CASE HISTORY
• A 7-year-old girl was referred from IGICH with a 20-day history of headache, vomiting, and fever, followed by altered sensorium. Initial evaluation at a local hospital included lumbar puncture, which revealed hypoglycorrhachia (CSF glucose: 11 mg/dL) and elevated CSF protein (160 mg/dL). CSF culture grew Kocuria rosea, and antibiotic therapy was initiated.
• Her past history was significant for chronic diarrhea of 3 years’ duration and esophageal candidiasis. Serum IgE levels were elevated, raising the suspicion of an underlying hyper-IgE syndrome.
• Immunological profile: Markedly elevated serum IgE (~7,694 IU/mL), low serum IgM (<16 mg/dL), and absolute lymphocyte count of ~1,240 cells/µL, raising suspicion for an underlying immunodeficiency, including hyper-IgE syndrome.
• On examination, the child was conscious and oriented (GCS: E4V5M6). Both pupils were equal and reactive to light. Motor examination revealed reduced power in the right upper limb (3/5) and right lower limb (4+/5), with power greater than 3/5 in the left upper and lower limbs. Head circumference was 91.5 cm and mid-upper arm circumference (MUAC) was 13.5 cm. There was no history of loss of consciousness, seizures, or limb weakness reported in the initial history.
• Neuroimaging raised initial suspicion of an infective lesion. Antitubercular therapy (ATT) and dexamethasone were subsequently initiated.
• She underwent left frontal craniotomy with ultrasound-guided aspiration of the suspected abscess on 23/08/2026, followed by re-exploration and resection on 27/08/2026. In view of neurological deterioration, worsening cerebral edema, and midline shift, she underwent extension of the craniotomy to a left frontotemporoparietal decompressive craniectomy with right frontal external ventricular drain (EVD) placement on 29/08/2026.
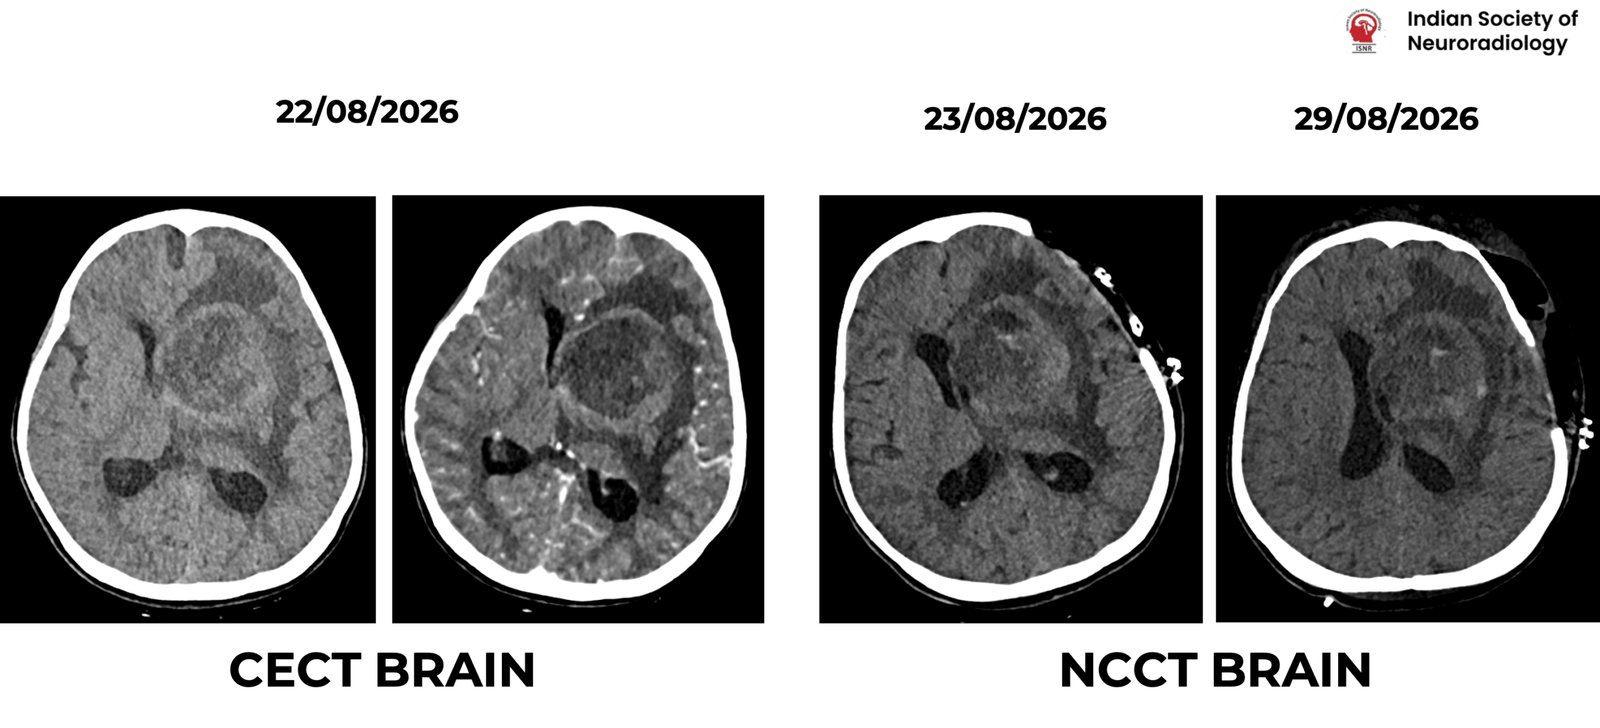


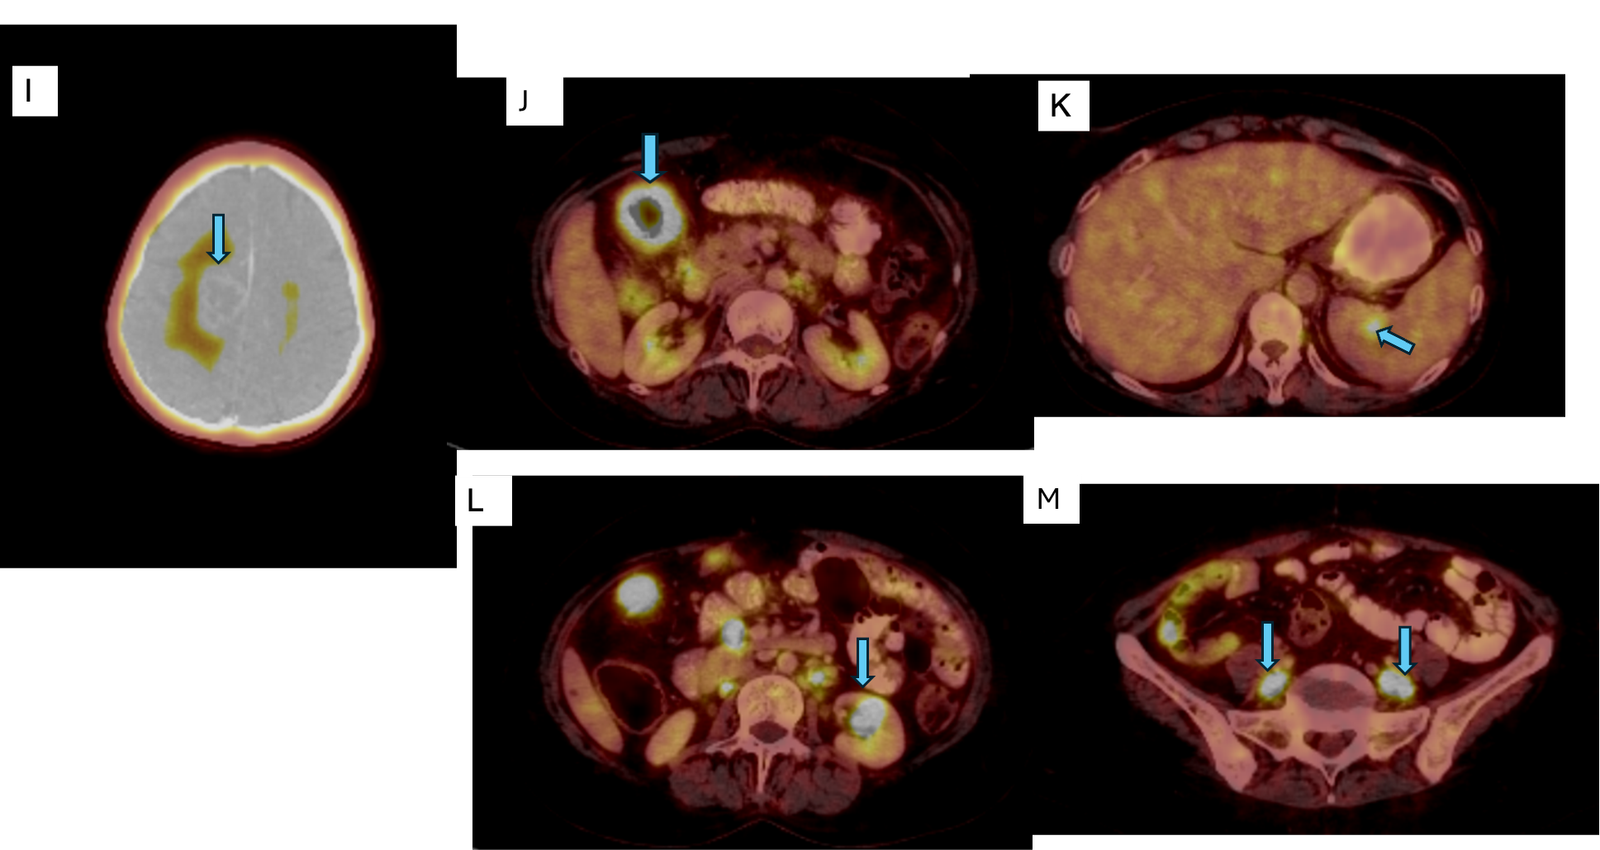
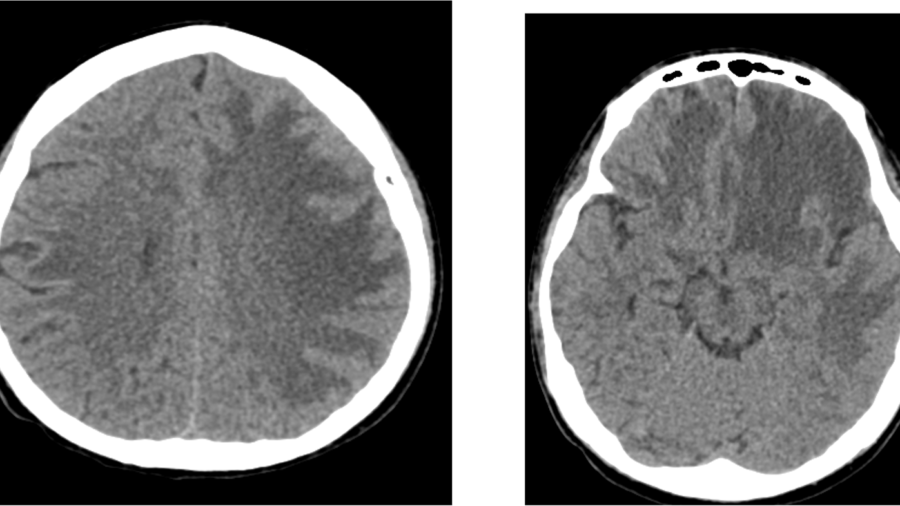
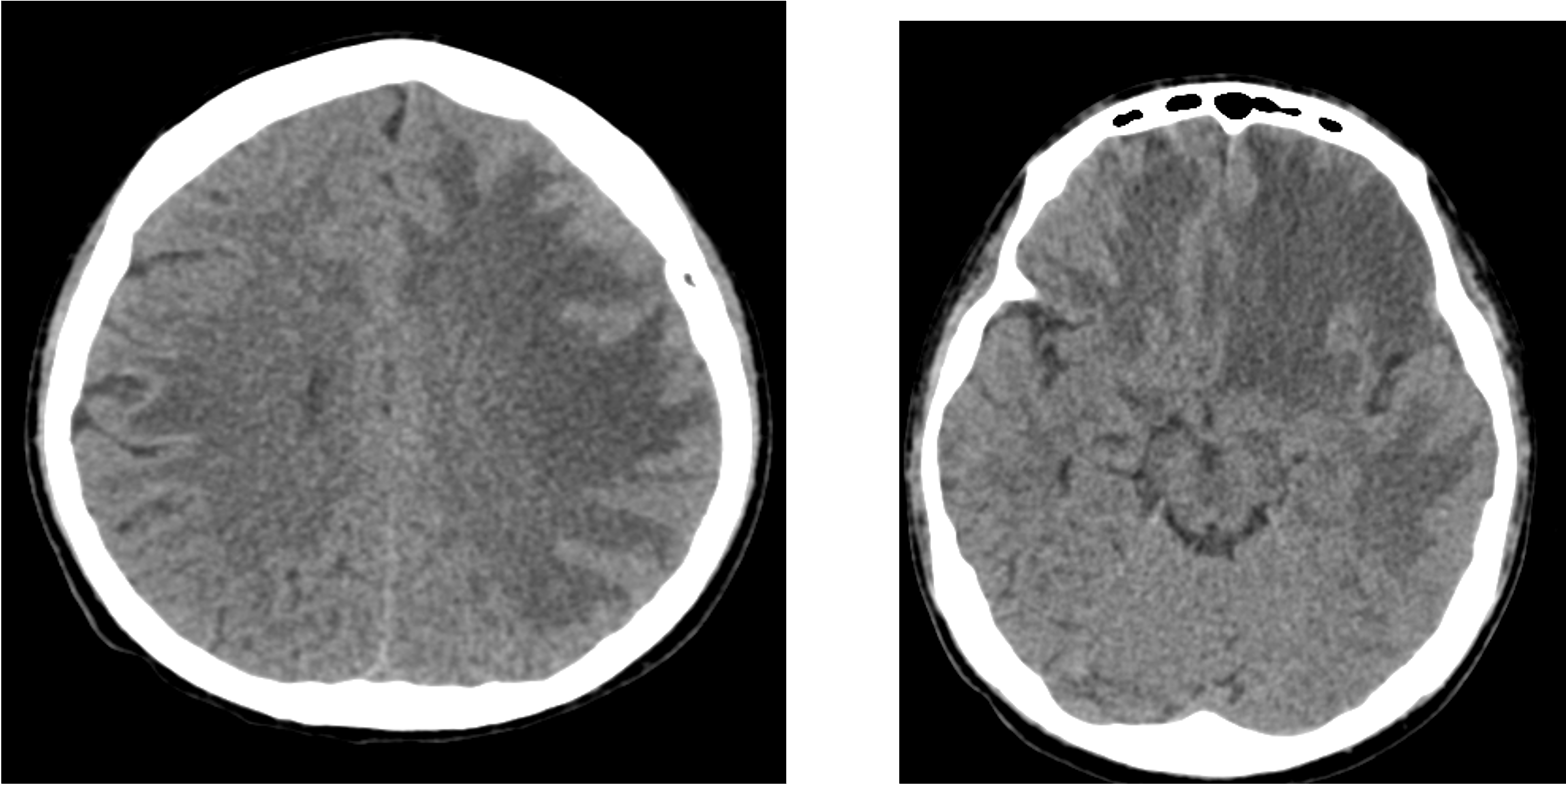
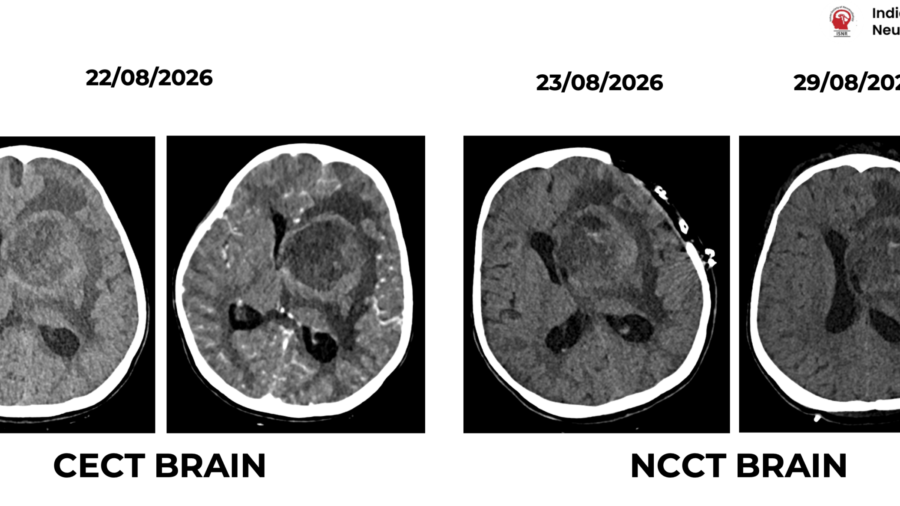
Serial CT BRAIN examinations (22/08/2026–29/08/2026)- Initial NCCT brain images dated 22/08/2026 demonstrate a left capsuloganglionic solid-cystic lesion with surrounding edema and mass effect. Post-contrast CECT images show peripheral ring enhancement. Follow-up NCCT images dated 23/08/2026 and 29/08/2026 demonstrate the lesion with persistent mass effect and interval postoperative hemorrhagic and decompressive craniectomy changes. Orange arrows indicate the lesion; green arrows indicate postoperative hemorrhagic changes.
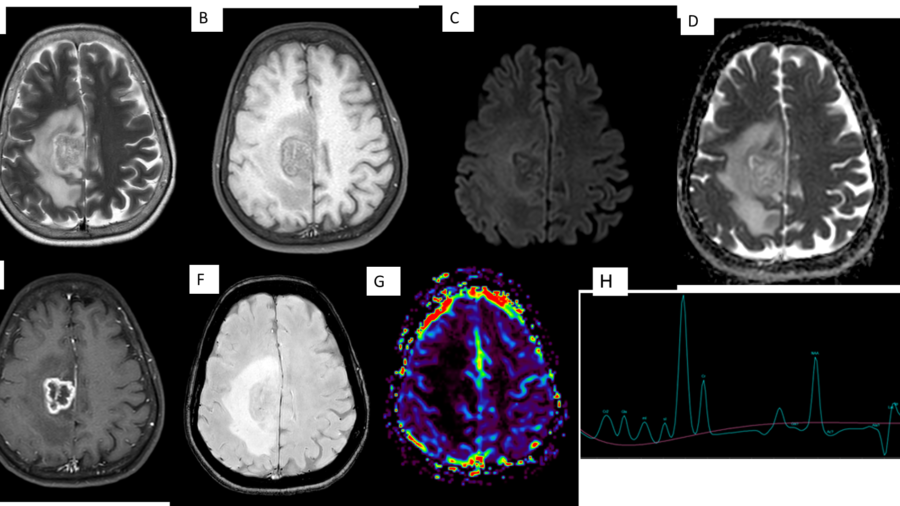
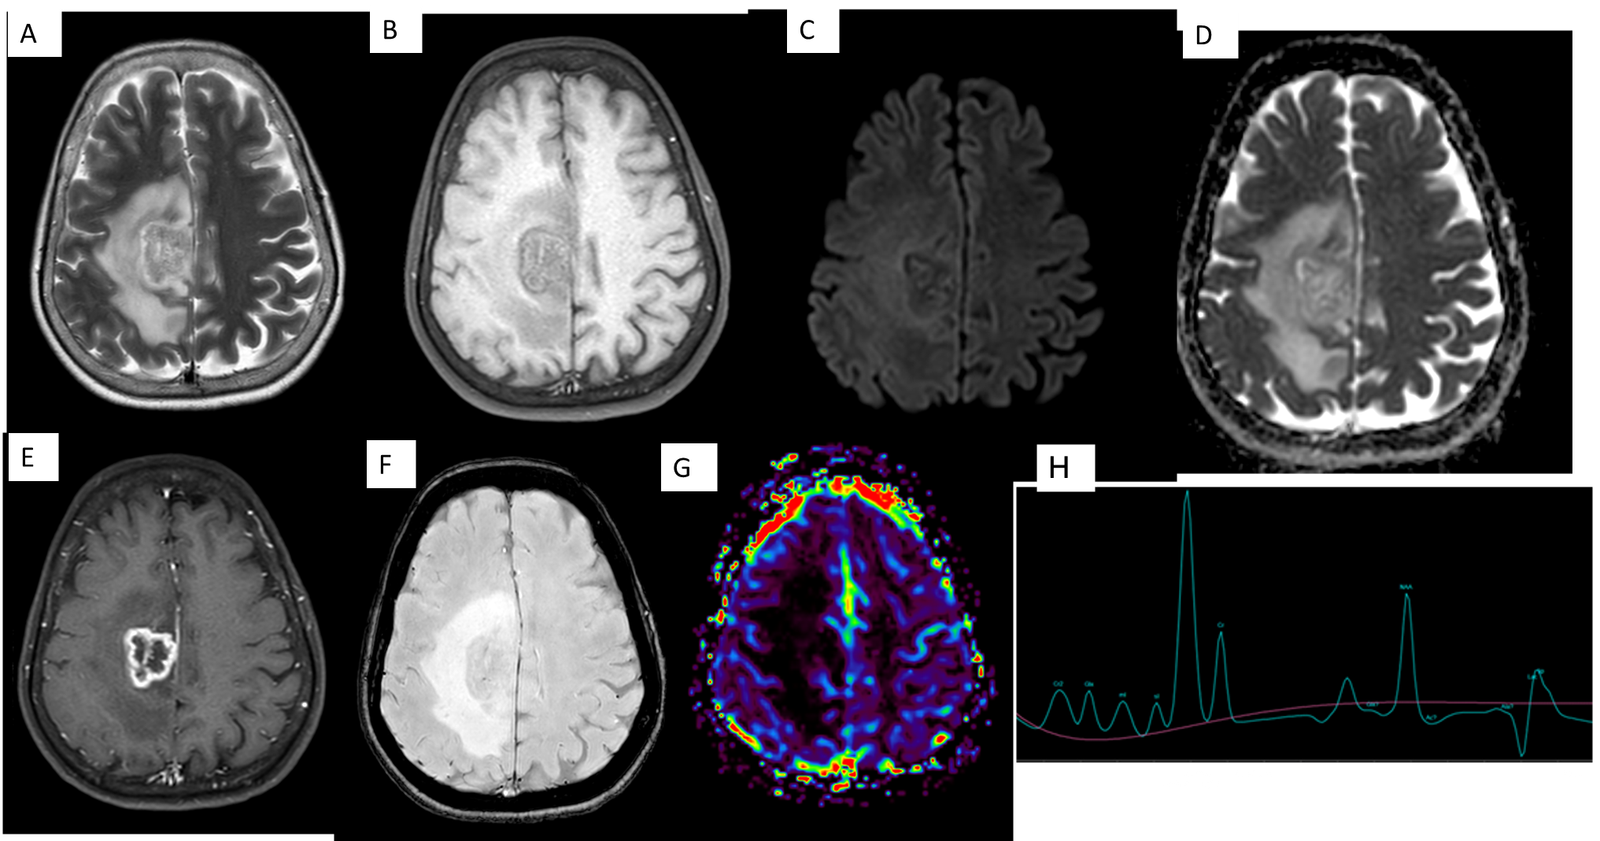
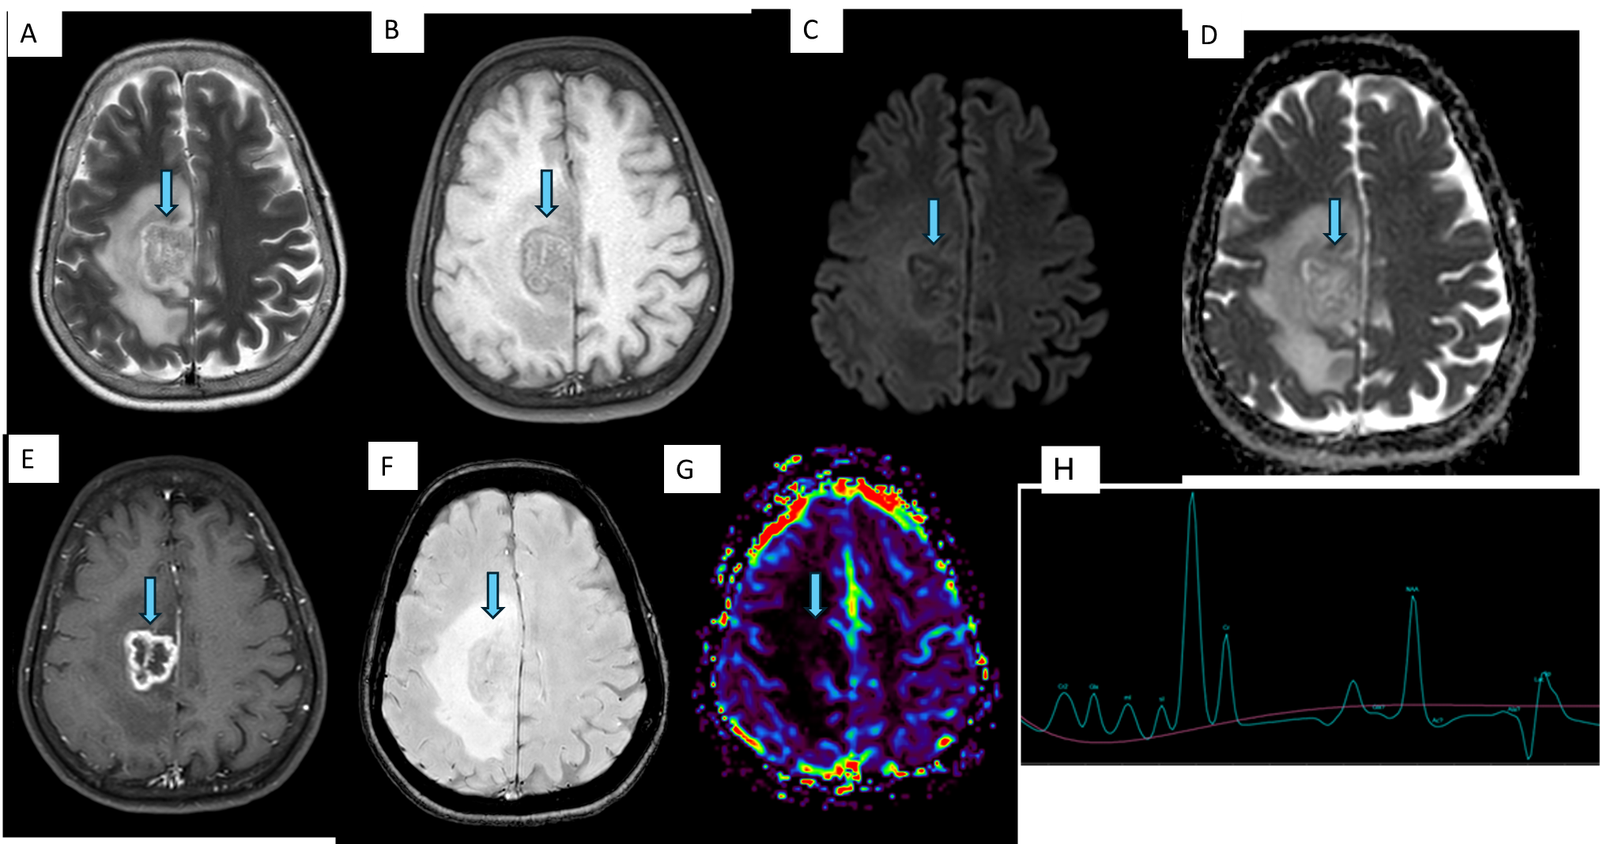
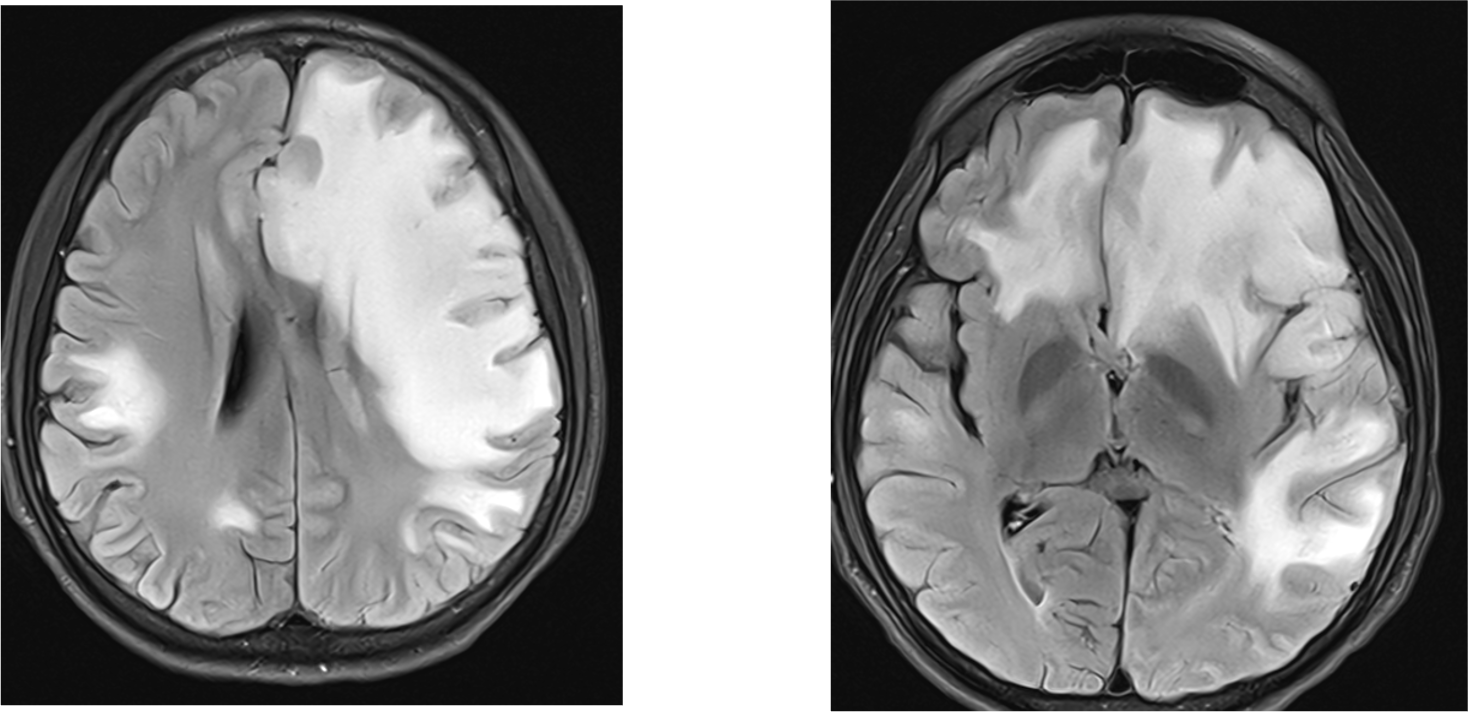
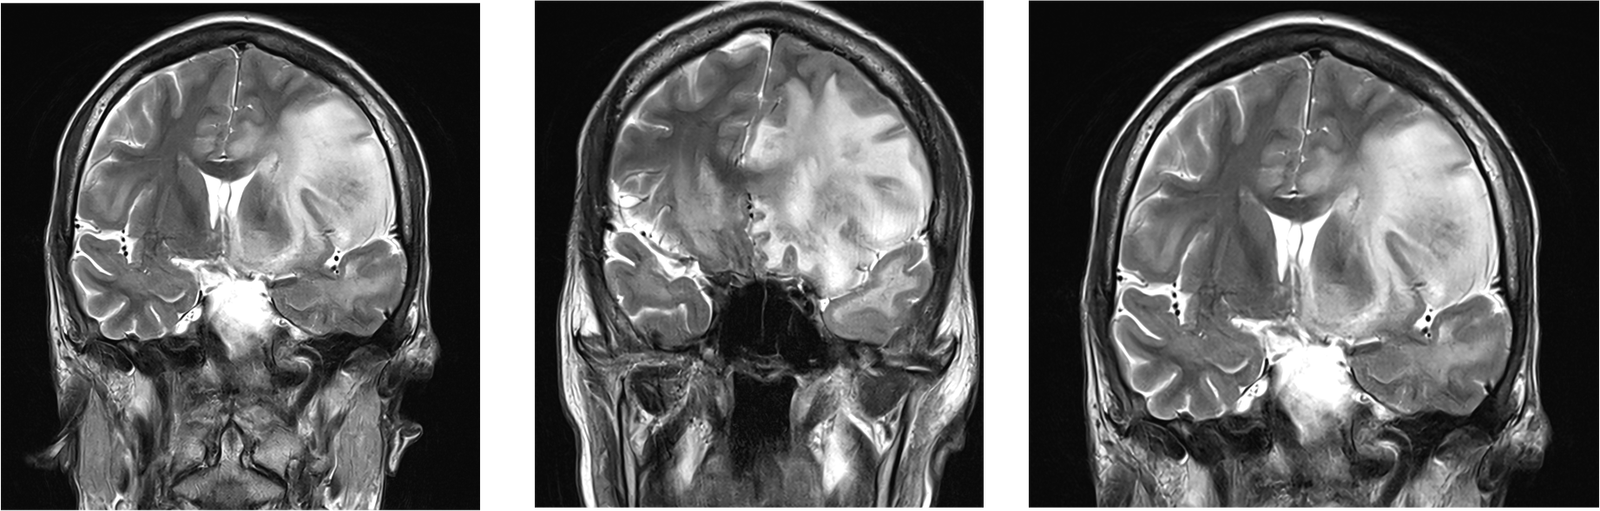
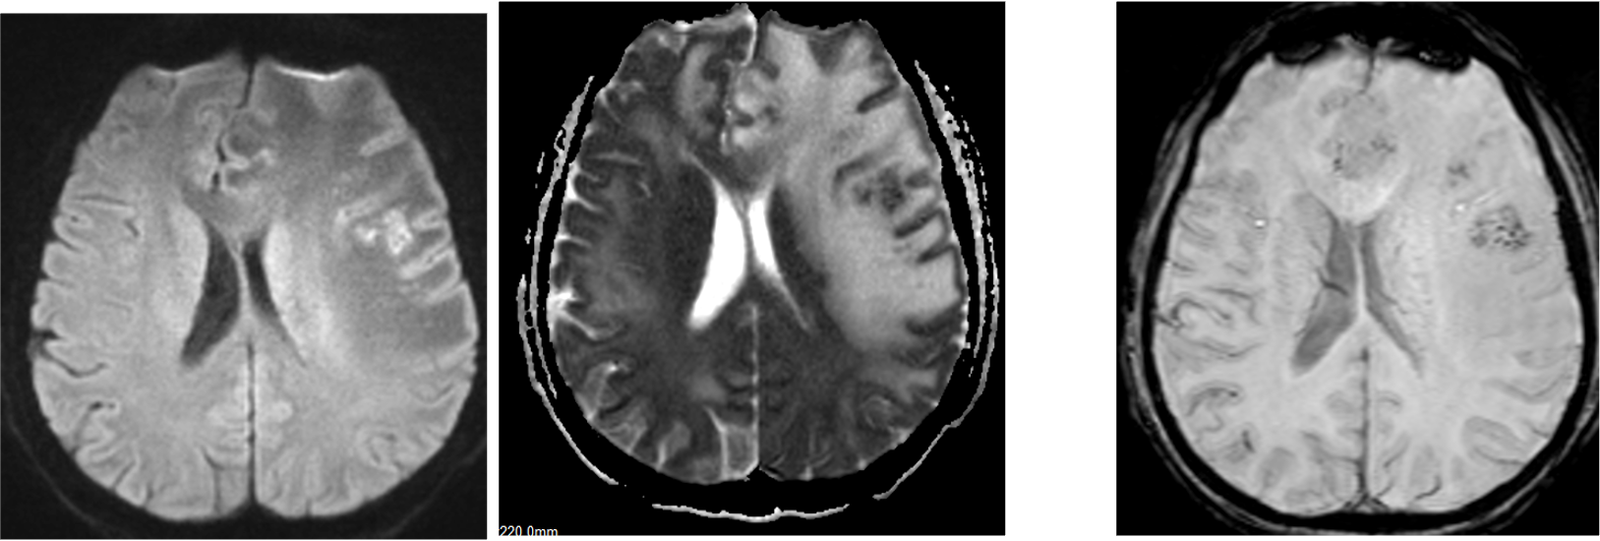
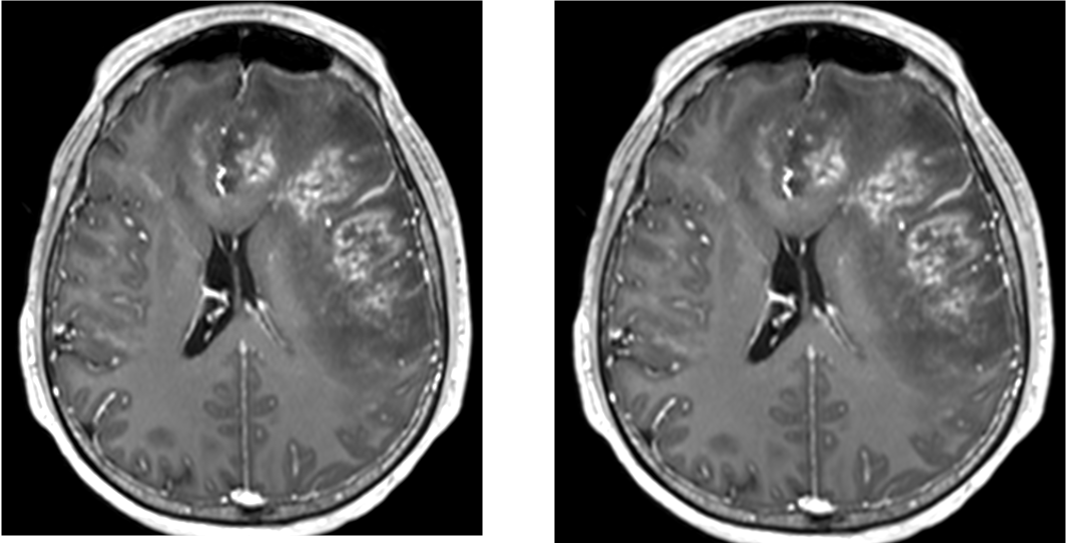
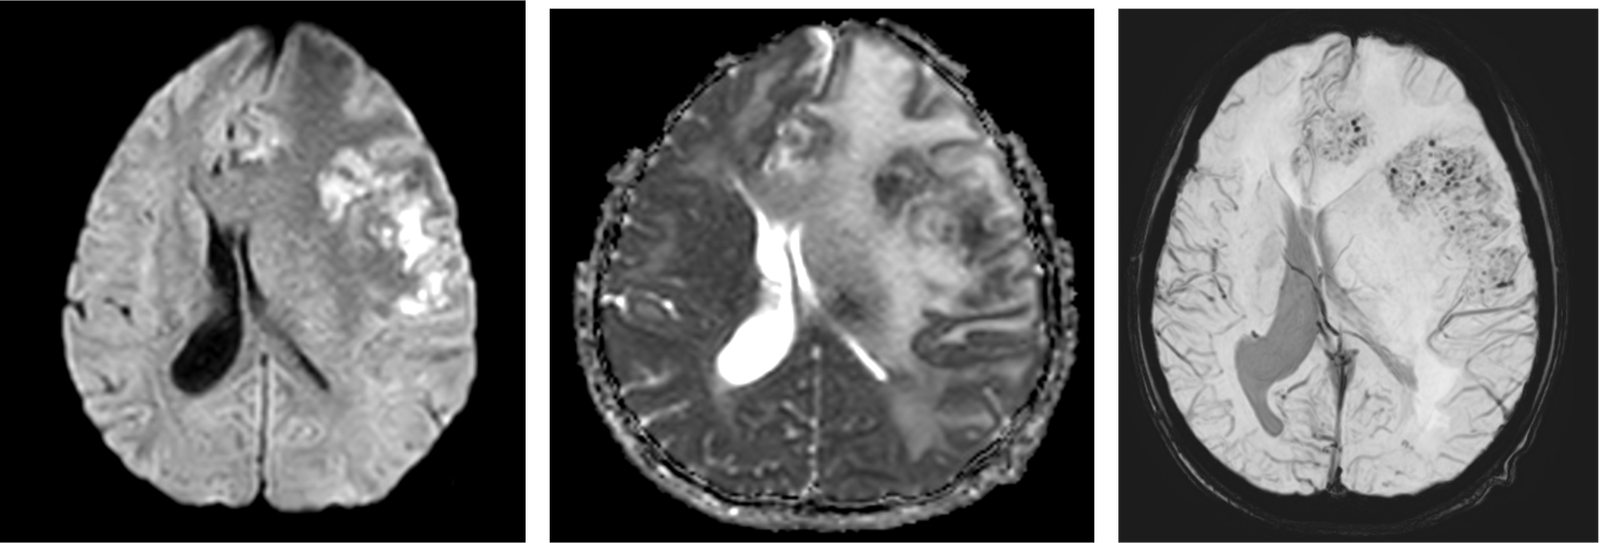
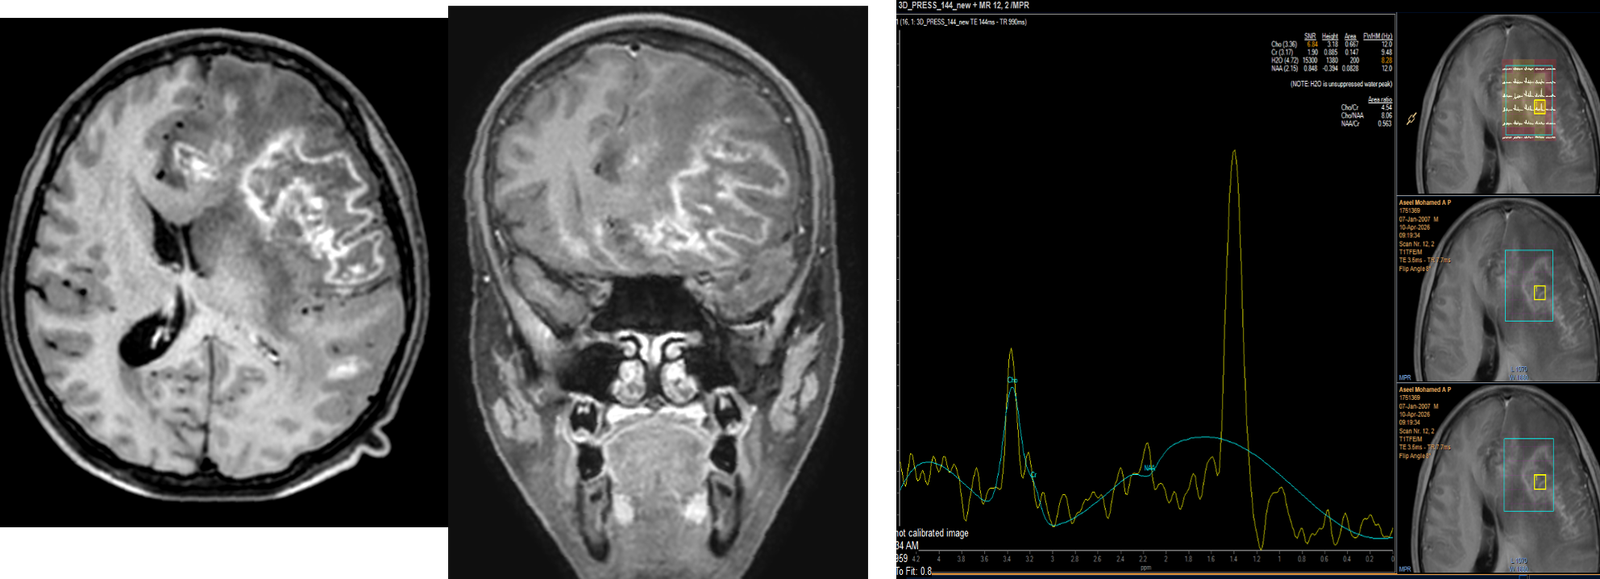
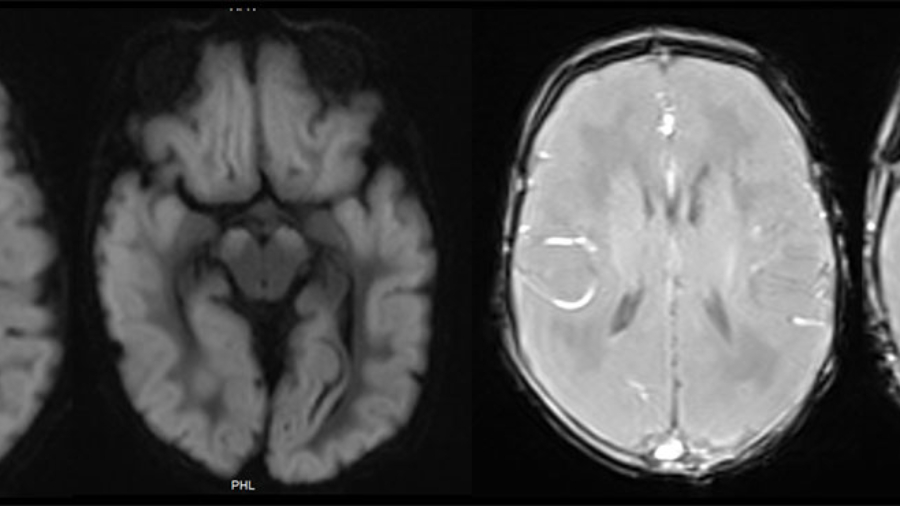
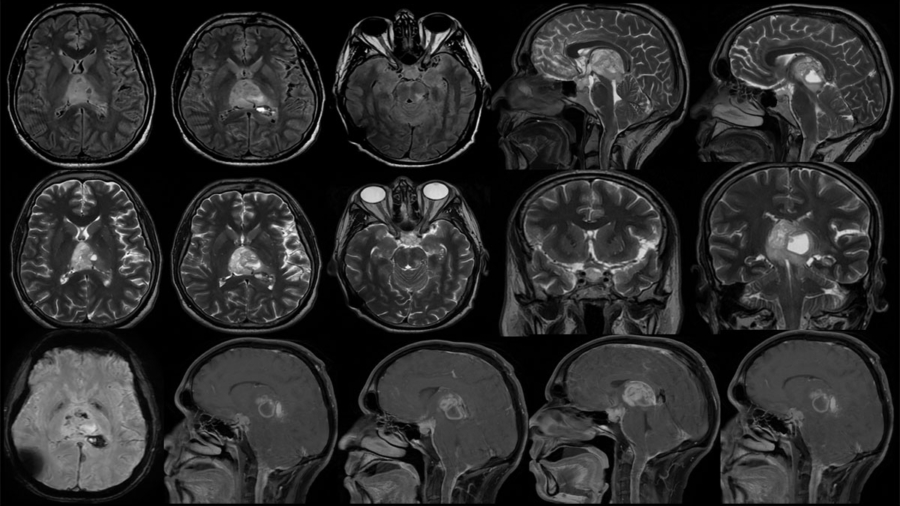
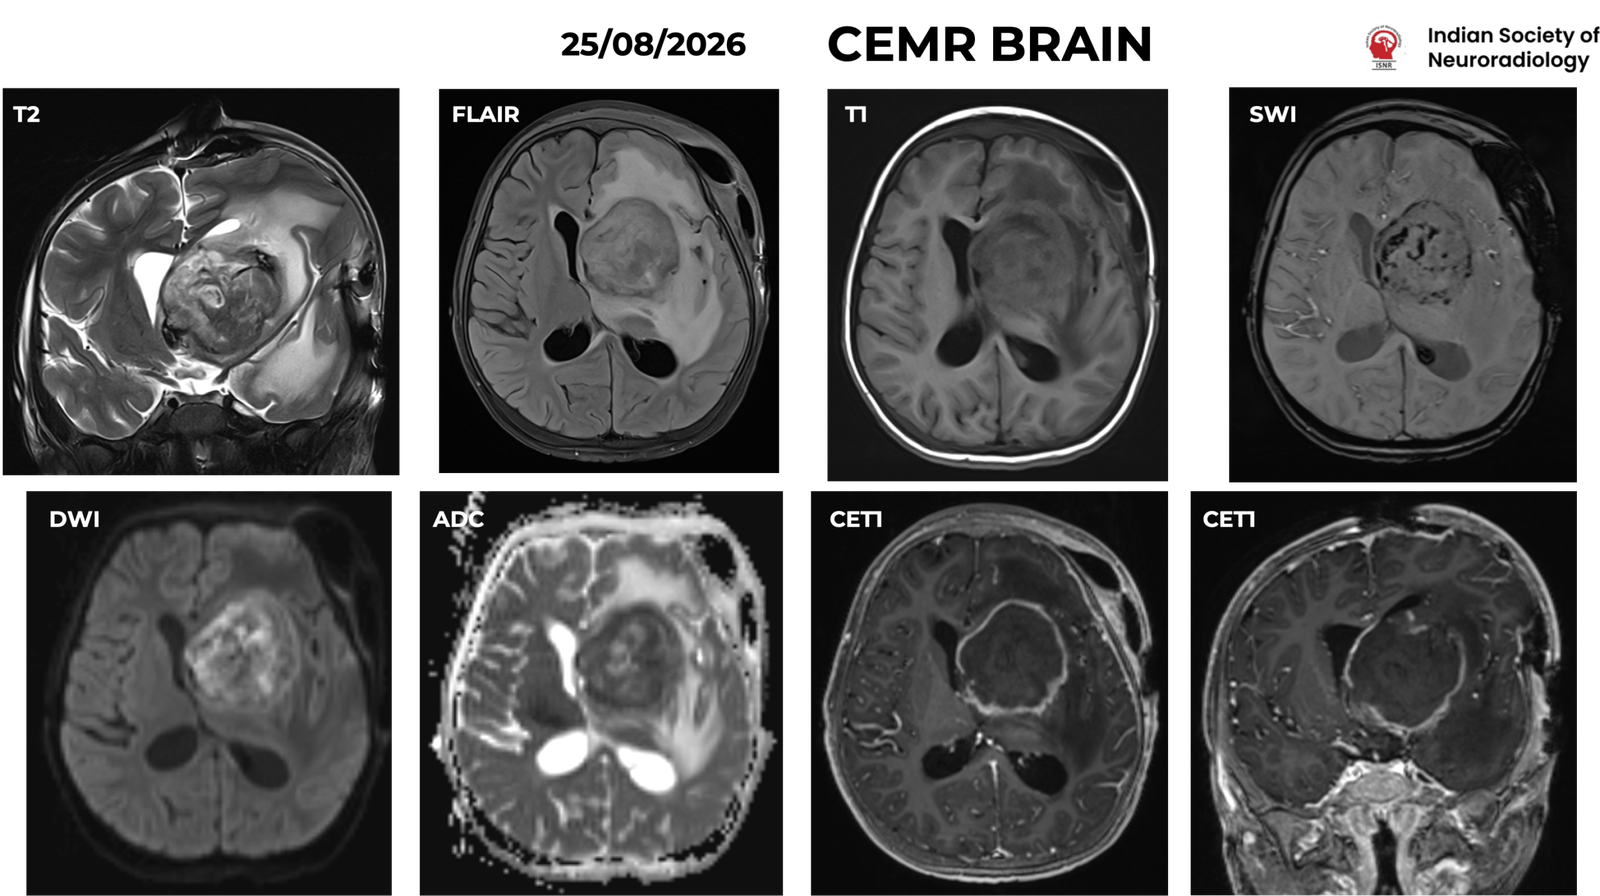
CEMRI BRAIN – A: Coronal T2; B: Axial FLAIR ; C: Axial T1; E: Axial SWI; F: DWI; G: ADC; H: Axial post-contrast T1;
I: Coronal post-contrast T1
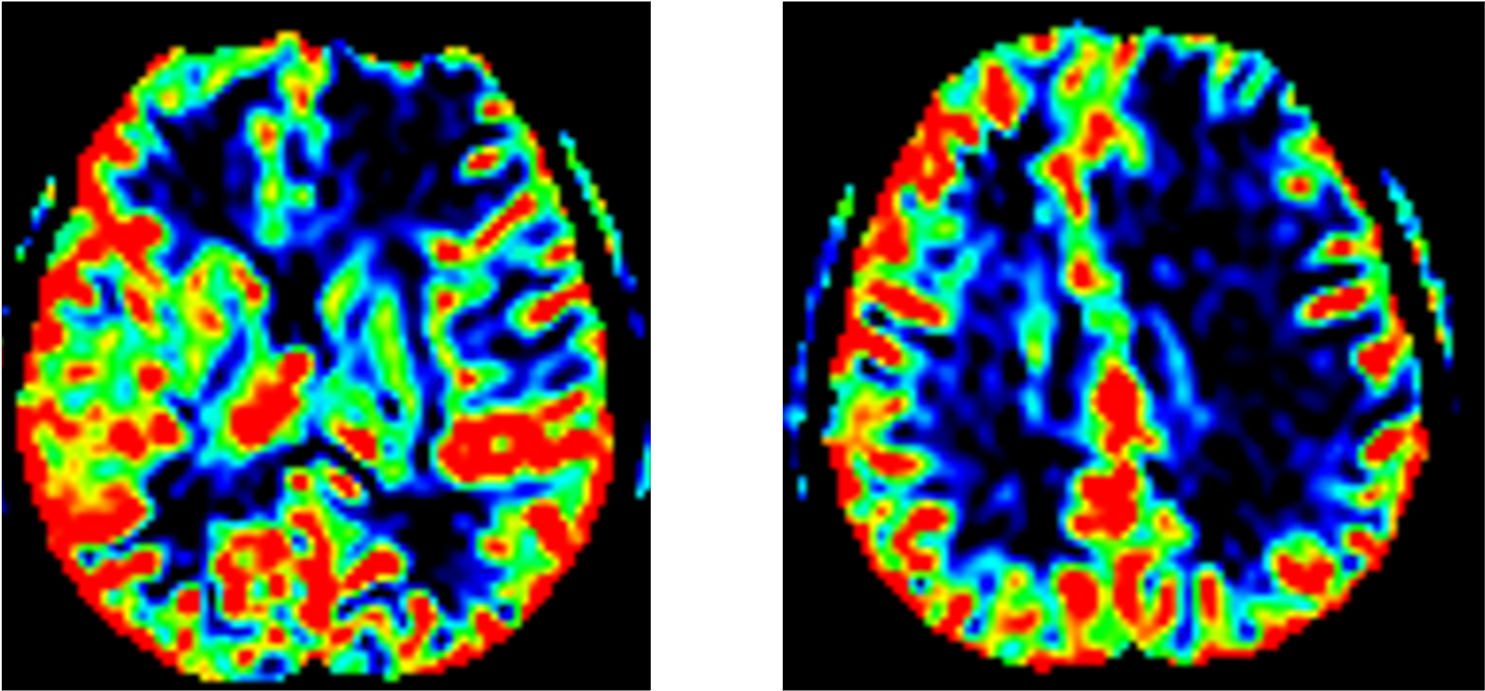
A large intra-axial space occupying lesion (orange arrows) is noted in left capsuloganglionic region demonstrating inhomogeneous T2 hypointense signals with few markedly T2 hypointense foci within the lesion suggesting, likely of hemorrhagic nature (green arrow). Foci of susceptibility blooming noted on SWI (green arrow) with marked intralesional diffusion restriction. On post-contrast imaging , the lesion demonstrates peripheral ring enhancement with central non enhancing core ( green arrow). Extensive surrounding edema and mass effect with effacement of locoregional sulcations, partial effacement of left lateral ventricle and focal midline shift to right side noted.
Provisional Diagnosis: Necrotizing infective etiology , likely fungal abscess
HISTOPATHOLOGY
Microscopic examination: Sections from the resected specimen show a high-grade lymphoid neoplasm composed of sheets of large atypical lymphoid cells with round nuclei, finely clumped chromatin, inconspicuous nucleoli, and scant eosinophilic cytoplasm. Mitotic activity is brisk, with numerous apoptotic bodies. The tumour cells demonstrate an angiocentric growth pattern around numerous thick-walled blood vessels. Areas of suppurative necrosis, hyalinised blood vessels, and scattered tingible-body macrophages are noted in the background.
Immunohistochemistry:
• LCA: Positive.
• CD20: Weakly positive in tumour cells.
• CD3: Highlights reactive T lymphocytes.
• ALK: Negative.
• CD99: Variably positive.
• MIB-1 (Ki-67) proliferation index: Approximately 75–80%.
Final histopathological diagnosis: High-grade B-cell non-Hodgkin lymphoma, involving the left capsuloganglionic region.

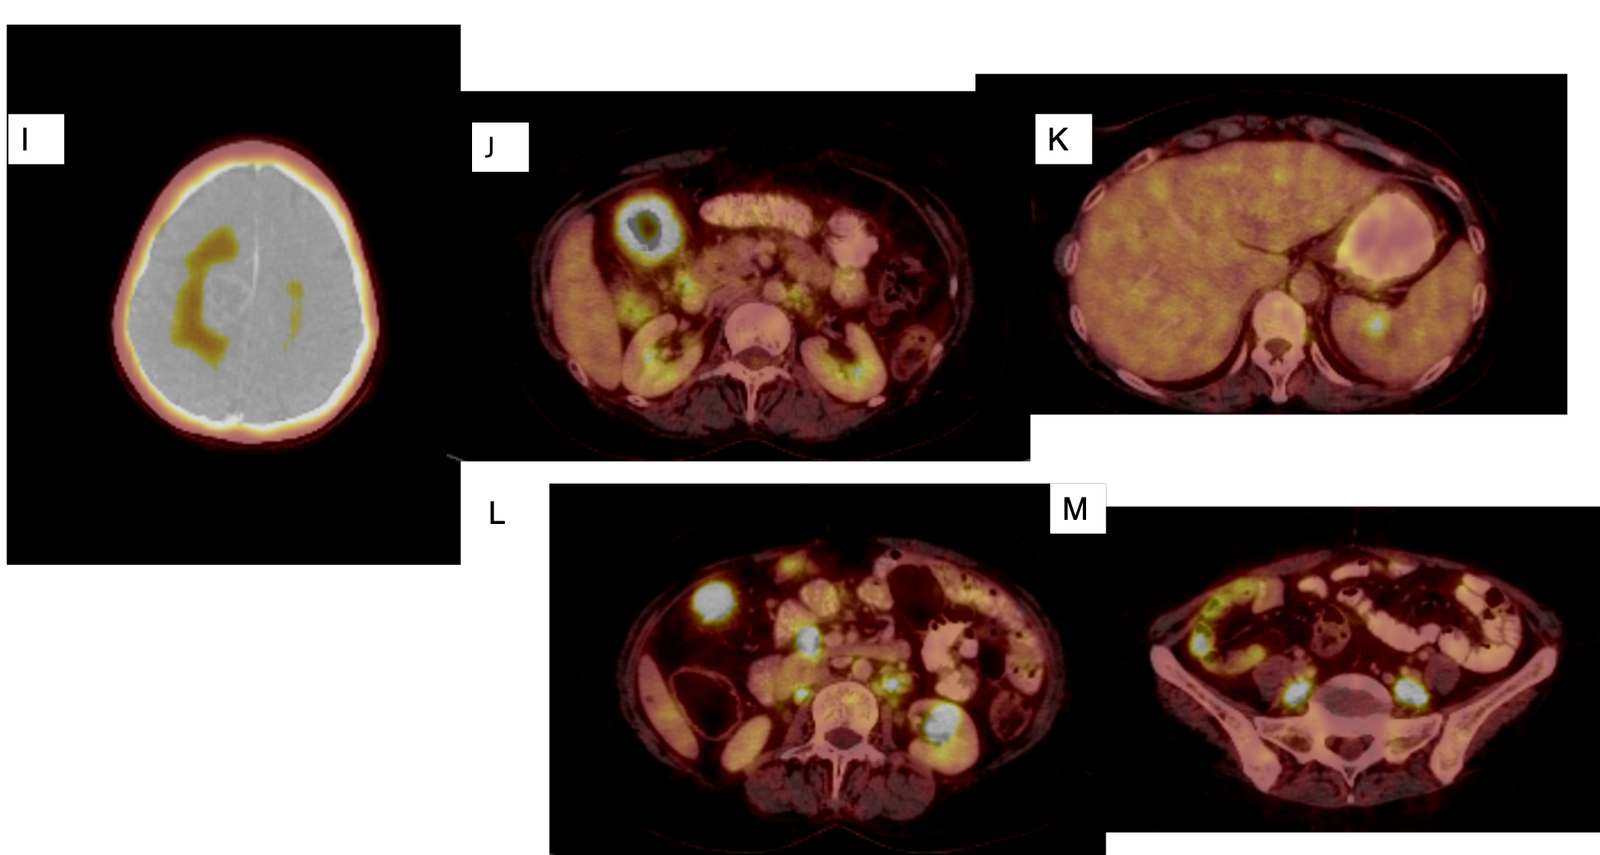
Hyper-IgE syndrome-associated CNS lymphoma
Autosomal recessive hyper-IgE syndrome due to DOCK8 deficiency is a combined immunodeficiency characterized by markedly elevated serum IgE, recurrent infections, eczema, and increased susceptibility to malignancy. DOCK8 plays an important role in lymphocyte cytoskeletal organization, migration, survival, and immune function. Impaired T-cell and natural killer cell function compromises immune surveillance, predisposing affected individuals to virus-associated malignancies, including B- and T-cell lymphomas. Lymphoma has been reported in approximately 5% of patients in the clinical series cited in the accompanying literature; however this figure refers to lymphoma overall, not specifically CNS lymphoma.
CNS lymphoma is a rare but important manifestation. Published case reports have described CNS lymphoma in patients with DOCK8 deficiency, sometimes initially mimicking an infective or inflammatory lesion on neuroimaging. In the present case, the combination of a ring-enhancing, diffusion-restricting capsuloganglionic lesion, markedly elevated serum IgE (7,694 IU/mL), low serum IgM, lymphopenia, and a homozygous pathogenic DOCK8 variant highlights the importance of considering CNS malignancy alongside infection in children with immunodeficiency. The initial infective presentation and suppurative necrosis further illustrate the potential diagnostic overlap. The association is biologically plausible, although CNS lymphoma remains an uncommon complication and should not be regarded as a characteristic imaging manifestation of DOCK8 deficiency.

STAT3-associated HIES (AD-HIES) is caused by dominant-negative STAT3 mutations and is characterized by recurrent staphylococcal infections, eczema, pneumatoceles, retained primary teeth, fractures, and connective-tissue abnormalities. CNS imaging associations include focal brain MRI hyperintensities (~75%) and Arnold–Chiari I malformation (~40%).
DOCK8 deficiency (AR-HIES) is a combined immunodeficiency characterized by severe viral skin infections, food allergies, eosinophilia, and increased risk of lymphoma and other malignancies. Unlike STAT3-HIES, skeletal and dental abnormalities are not typical; severe viral susceptibility and malignancy risk are more prominent.
Other CNS manifestations of hyper-IgE syndrome
• Focal brain MRI hyperintensities: Reported in approximately 75% of patients with STAT3-associated HIES.
• Arnold–Chiari type I malformation: Reported in approximately 40% of patients with STAT3-associated HIES.
• Cerebrovascular abnormalities: CNS vasculitis, lacunar infarctions, cerebral aneurysms, and stroke.
• CNS infections: Meningitis, encephalitis, and bacterial or fungal brain abscesses, particularly in DOCK8 deficiency.
• Demyelinating disorders: Inflammatory demyelination and acute disseminated encephalomyelitis-like presentations have been reported in DOCK8 deficiency.
• Progressive multifocal leukoencephalopathy (PML): A rare opportunistic CNS complication reported in DOCK8 deficiency.
These complications reflect the diverse consequences of immune dysfunction and, in some patients, vascular injury.
References
1. Freeman AF, Holland SM. Clinical manifestations, etiology, and pathogenesis of the hyper-IgE syndromes. Pediatr Res. 2009;65(5 Pt 2):32R–37R. doi:10.1203/PDR.0b013e31819dc8c5.
2. Engelhardt KR, et al. The extended clinical phenotype of 64 patients with dedicator of cytokinesis 8 deficiency. J Allergy Clin Immunol. 2015;136(2):402–412. doi:10.1016/j.jaci.2014.12.1945.
3. Biggs CM, Keles S, Chatila TA. DOCK8 deficiency: Insights into pathophysiology, clinical features and management. Clin Immunol. 2017;181:75–82. doi:10.1016/j.clim.2017.06.003.
4. AlKhater SA. CNS vasculitis and stroke as a complication of DOCK8 deficiency: a case report. BMC Neurol. 2016;16:54. doi:10.1186/s12883-016-0578-3.
5. Eroglu FK, et al. A case of DOCK8 deficiency and Epstein–Barr virus associated intracranial lymphoma. Allergy. 2011;66:546. Conference abstract.