Picture 1

October 2026

CASE HISTORY

• A 7-year-old girl was referred from IGICH with a 20-day history of headache, vomiting, and fever, followed by altered sensorium. Initial evaluation at a local hospital included lumbar puncture, which revealed hypoglycorrhachia (CSF glucose: 11 mg/dL) and elevated CSF protein (160 mg/dL). CSF culture grew Kocuria rosea, and antibiotic therapy was initiated.

• Her past history was significant for chronic diarrhea of 3 years’ duration and esophageal candidiasis. Serum IgE levels were elevated, raising the suspicion of an underlying hyper-IgE syndrome.

• Immunological profile: Markedly elevated serum IgE (~7,694 IU/mL), low serum IgM (<16 mg/dL), and absolute lymphocyte count of ~1,240 cells/µL, raising suspicion for an underlying immunodeficiency, including hyper-IgE syndrome.

• On examination, the child was conscious and oriented (GCS: E4V5M6). Both pupils were equal and reactive to light. Motor examination revealed reduced power in the right upper limb (3/5) and right lower limb (4+/5), with power greater than 3/5 in the left upper and lower limbs. Head circumference was 91.5 cm and mid-upper arm circumference (MUAC) was 13.5 cm. There was no history of loss of consciousness, seizures, or limb weakness reported in the initial history.

• Neuroimaging raised initial suspicion of an infective lesion. Antitubercular therapy (ATT) and dexamethasone were subsequently initiated.

• She underwent left frontal craniotomy with ultrasound-guided aspiration of the suspected abscess on 23/08/2026, followed by re-exploration and resection on 27/08/2026. In view of neurological deterioration, worsening cerebral edema, and midline shift, she underwent extension of the craniotomy to a left frontotemporoparietal decompressive craniectomy with right frontal external ventricular drain (EVD) placement on 29/08/2026.
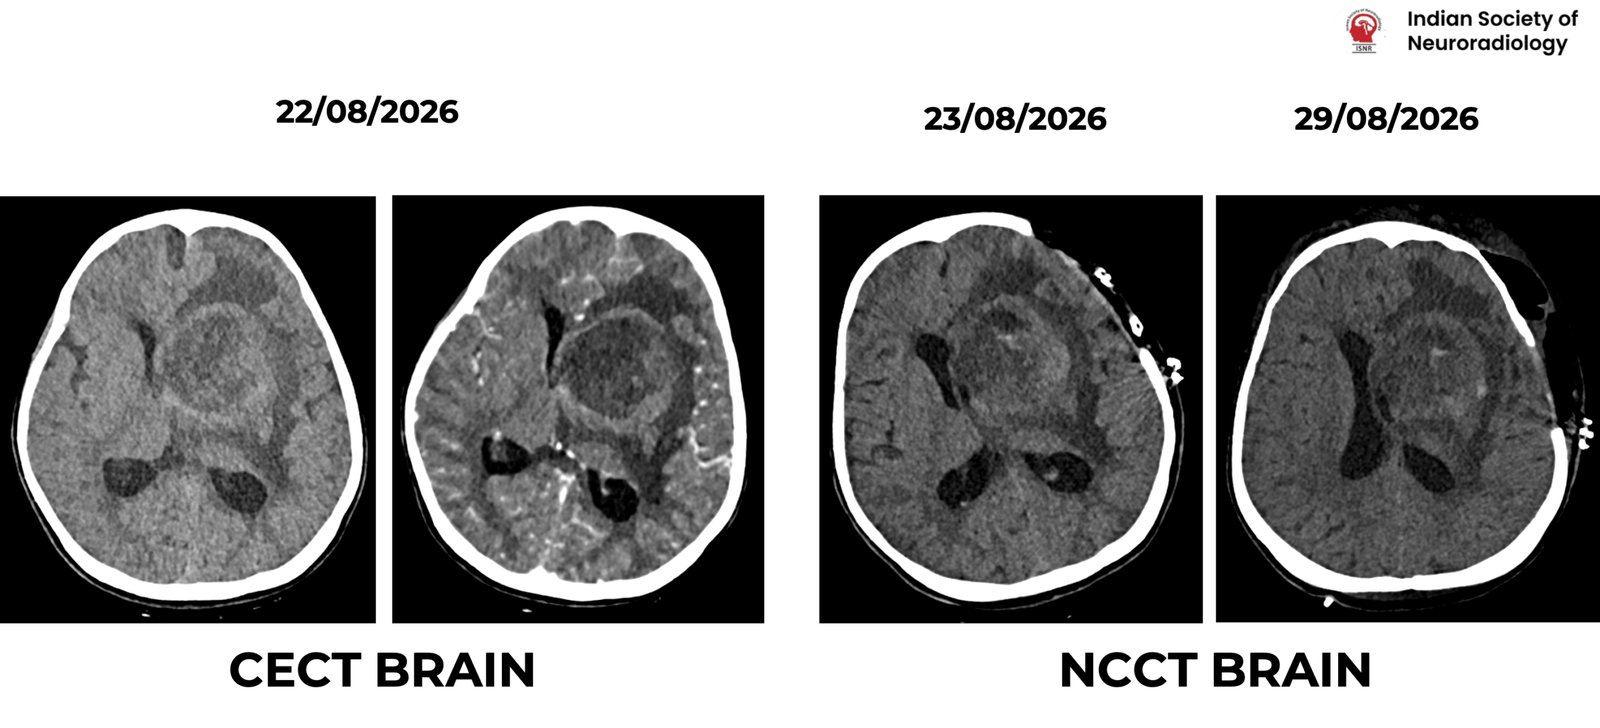
Serial CT BRAIN examinations (22/08/2026–29/08/2026)- Initial NCCT brain images dated 22/08/2026 demonstrate a left capsuloganglionic solid-cystic lesion with surrounding edema and mass effect. Post-contrast CECT images show peripheral ring enhancement. Follow-up NCCT images dated 23/08/2026 and 29/08/2026 demonstrate the lesion with persistent mass effect and interval postoperative hemorrhagic and decompressive craniectomy changes. Orange arrows indicate the lesion; green arrows indicate postoperative hemorrhagic changes.

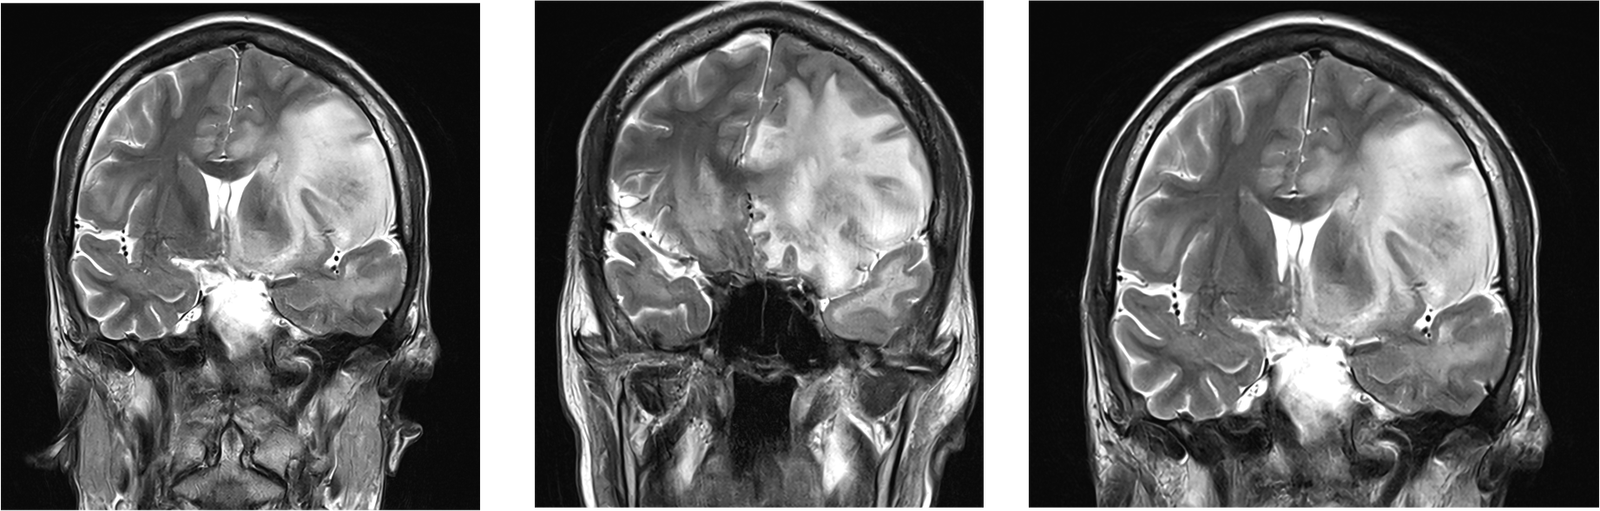
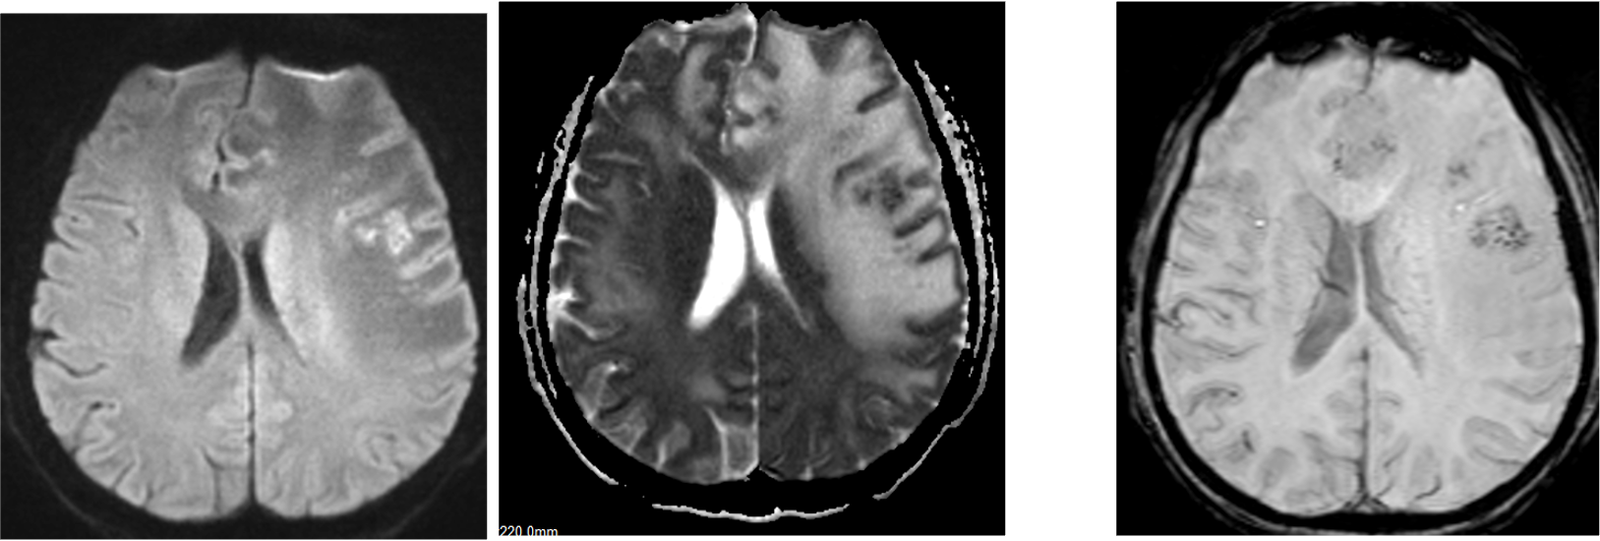
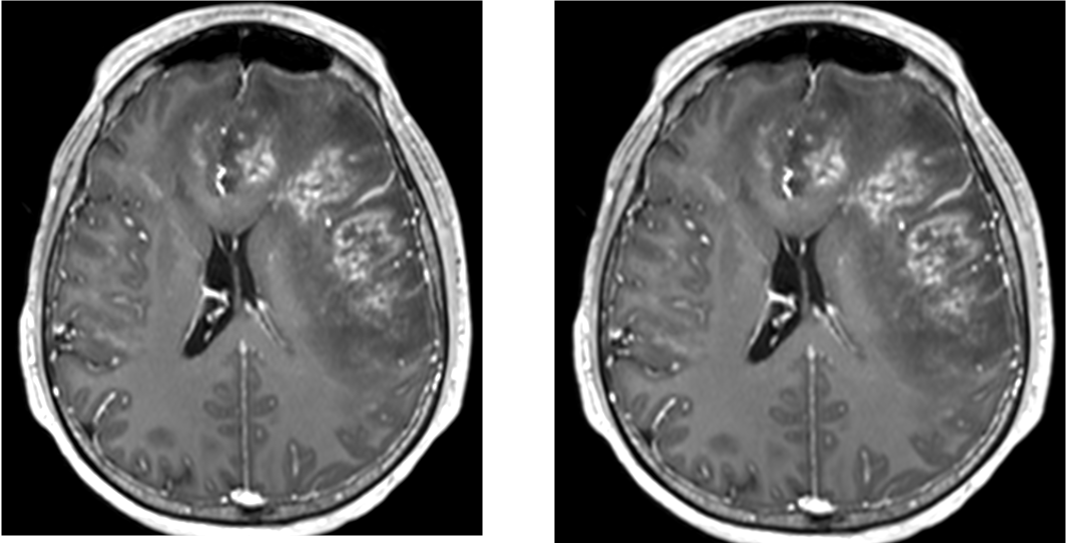
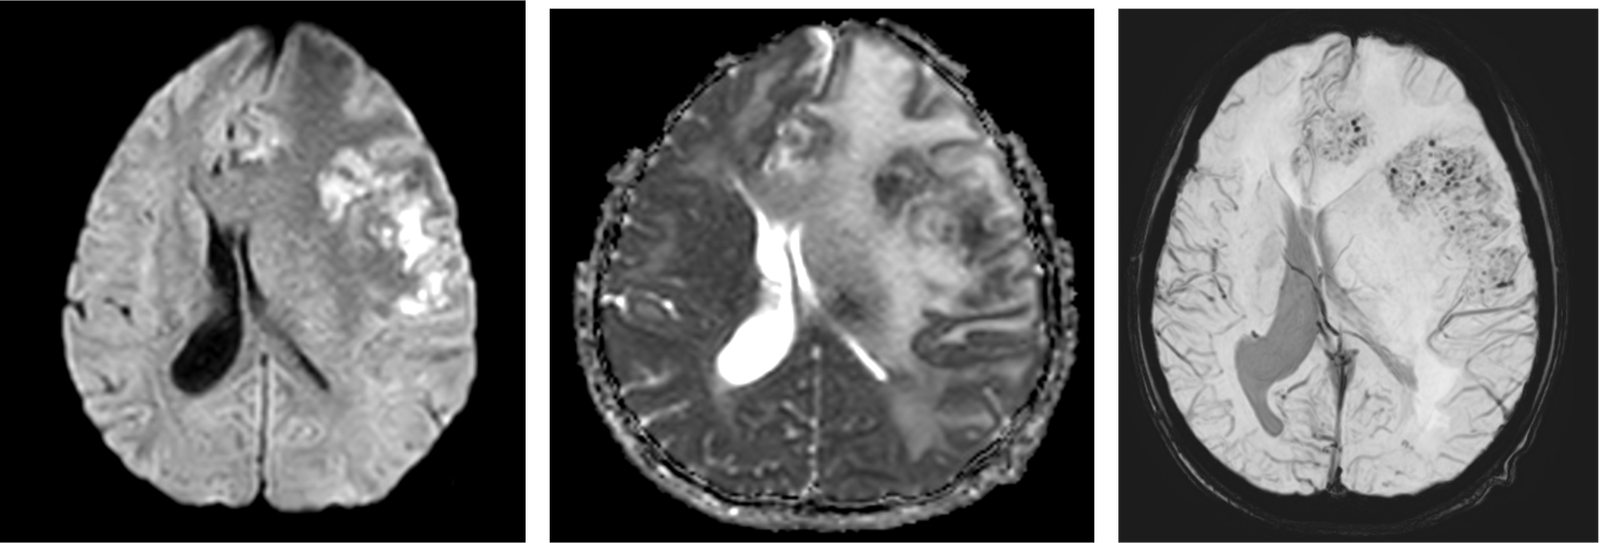
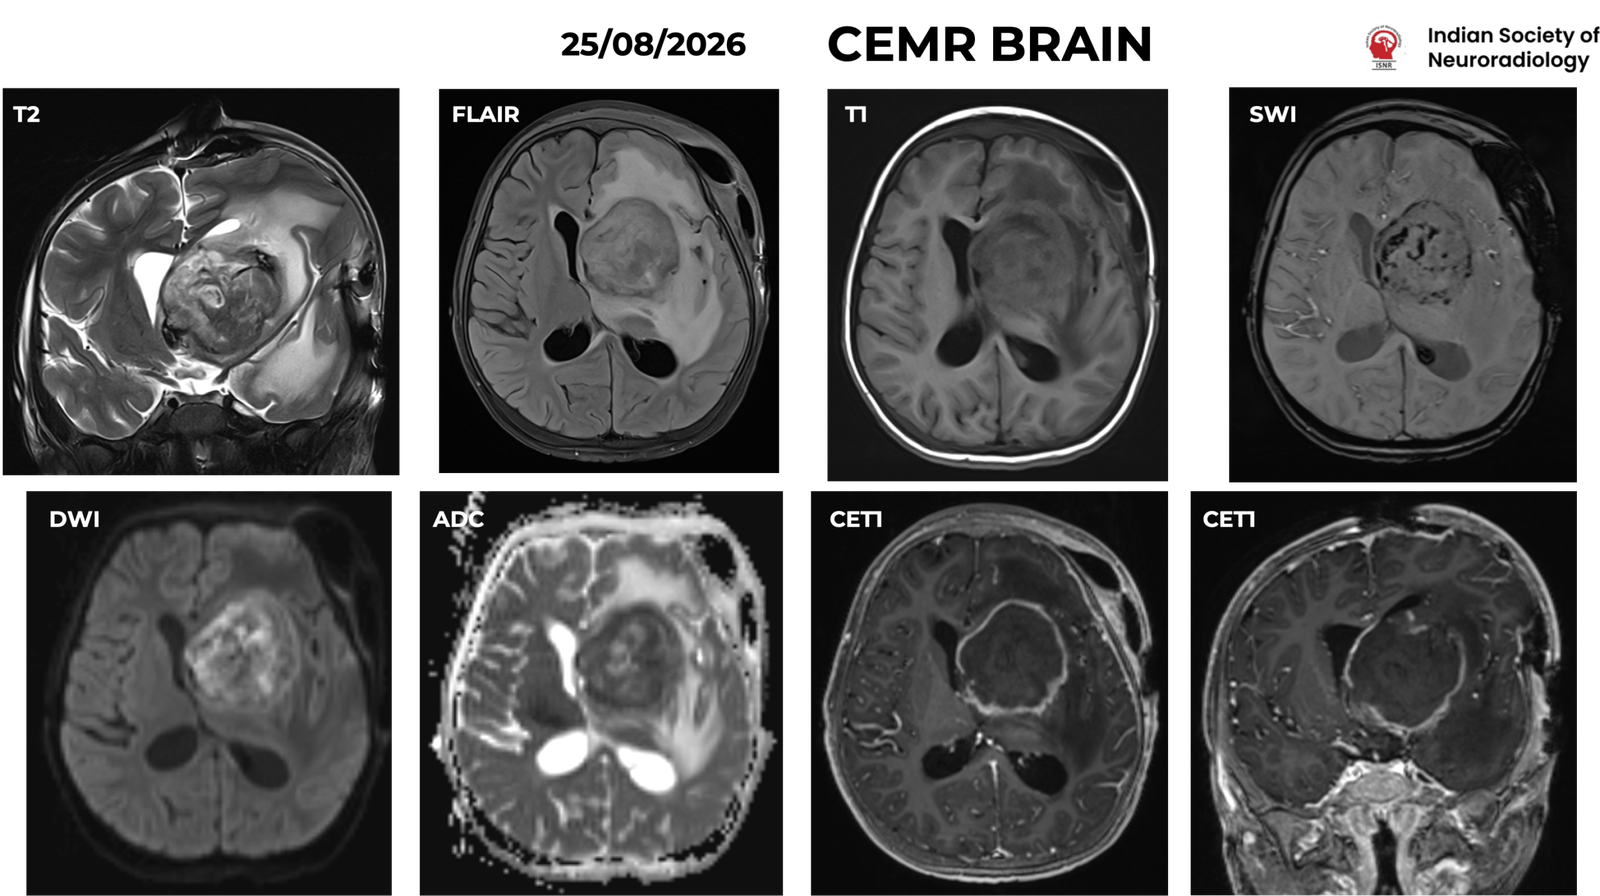
CEMRI BRAIN – A: Coronal T2; B: Axial FLAIR ; C: Axial T1; E: Axial SWI; F: DWI; G: ADC; H: Axial post-contrast T1;

I: Coronal post-contrast T1

A large intra-axial space occupying lesion (orange arrows) is noted in left capsuloganglionic region demonstrating inhomogeneous T2 hypointense signals with few markedly T2 hypointense foci within the lesion suggesting, likely of hemorrhagic nature (green arrow). Foci of susceptibility blooming noted on SWI (green arrow) with marked intralesional diffusion restriction. On post-contrast imaging , the lesion demonstrates peripheral ring enhancement with central non enhancing core ( green arrow). Extensive surrounding edema  and mass effect with effacement of locoregional sulcations, partial effacement of left lateral ventricle and focal midline shift to right side noted.

Provisional Diagnosis: Necrotizing infective etiology , likely fungal abscess

HISTOPATHOLOGY

Microscopic examination: Sections from the resected specimen show a high-grade lymphoid neoplasm composed of sheets of large atypical lymphoid cells with round nuclei, finely clumped chromatin, inconspicuous nucleoli, and scant eosinophilic cytoplasm. Mitotic activity is brisk, with numerous apoptotic bodies. The tumour cells demonstrate an angiocentric growth pattern around numerous thick-walled blood vessels. Areas of suppurative necrosis, hyalinised blood vessels, and scattered tingible-body macrophages are noted in the background.

Immunohistochemistry:

• LCA: Positive.

• CD20: Weakly positive in tumour cells.

• CD3: Highlights reactive T lymphocytes.

• ALK: Negative.

• CD99: Variably positive.

• MIB-1 (Ki-67) proliferation index: Approximately 75–80%.

Final histopathological diagnosis: High-grade B-cell non-Hodgkin lymphoma, involving the left capsuloganglionic region.

Hyper-IgE syndrome-associated CNS lymphoma

Autosomal recessive hyper-IgE syndrome due to DOCK8 deficiency is a combined immunodeficiency characterized by markedly elevated serum IgE, recurrent infections, eczema, and increased susceptibility to malignancy. DOCK8 plays an important role in lymphocyte cytoskeletal organization, migration, survival, and immune function. Impaired T-cell and natural killer cell function compromises immune surveillance, predisposing affected individuals to virus-associated malignancies, including B- and T-cell lymphomas. Lymphoma has been reported in approximately 5% of patients in the clinical series cited in the accompanying literature; however this figure refers to lymphoma overall, not specifically CNS lymphoma.

CNS lymphoma is a rare but important manifestation. Published case reports have described CNS lymphoma in patients with DOCK8 deficiency, sometimes initially mimicking an infective or inflammatory lesion on neuroimaging. In the present case, the combination of a ring-enhancing, diffusion-restricting capsuloganglionic lesion, markedly elevated serum IgE (7,694 IU/mL), low serum IgM, lymphopenia, and a homozygous pathogenic DOCK8 variant highlights the importance of considering CNS malignancy alongside infection in children with immunodeficiency. The initial infective presentation and suppurative necrosis further illustrate the potential diagnostic overlap. The association is biologically plausible, although CNS lymphoma remains an uncommon complication and should not be regarded as a characteristic imaging manifestation of DOCK8 deficiency.

STAT3-associated HIES (AD-HIES) is caused by dominant-negative STAT3 mutations and is characterized by recurrent staphylococcal infections, eczema, pneumatoceles, retained primary teeth, fractures, and connective-tissue abnormalities. CNS imaging associations include focal brain MRI hyperintensities (~75%) and Arnold–Chiari I malformation (~40%).

DOCK8 deficiency (AR-HIES) is a combined immunodeficiency characterized by severe viral skin infections, food allergies, eosinophilia, and increased risk of lymphoma and other malignancies. Unlike STAT3-HIES, skeletal and dental abnormalities are not typical; severe viral susceptibility and malignancy risk are more prominent.

Other CNS manifestations of hyper-IgE syndrome

• Focal brain MRI hyperintensities: Reported in approximately 75% of patients with STAT3-associated HIES.

• Arnold–Chiari type I malformation: Reported in approximately 40% of patients with STAT3-associated HIES.

• Cerebrovascular abnormalities: CNS vasculitis, lacunar infarctions, cerebral aneurysms, and stroke.

• CNS infections: Meningitis, encephalitis, and bacterial or fungal brain abscesses, particularly in DOCK8 deficiency.

• Demyelinating disorders: Inflammatory demyelination and acute disseminated encephalomyelitis-like presentations have been reported in DOCK8 deficiency.

• Progressive multifocal leukoencephalopathy (PML): A rare opportunistic CNS complication reported in DOCK8 deficiency.

These complications reflect the diverse consequences of immune dysfunction and, in some patients, vascular injury.

References

1. Freeman AF, Holland SM. Clinical manifestations, etiology, and pathogenesis of the hyper-IgE syndromes. Pediatr Res. 2009;65(5 Pt 2):32R–37R. doi:10.1203/PDR.0b013e31819dc8c5.

2. Engelhardt KR, et al. The extended clinical phenotype of 64 patients with dedicator of cytokinesis 8 deficiency. J Allergy Clin Immunol. 2015;136(2):402–412. doi:10.1016/j.jaci.2014.12.1945.

3. Biggs CM, Keles S, Chatila TA. DOCK8 deficiency: Insights into pathophysiology, clinical features and management. Clin Immunol. 2017;181:75–82. doi:10.1016/j.clim.2017.06.003.

4. AlKhater SA. CNS vasculitis and stroke as a complication of DOCK8 deficiency: a case report. BMC Neurol. 2016;16:54. doi:10.1186/s12883-016-0578-3.

5. Eroglu FK, et al. A case of DOCK8 deficiency and Epstein–Barr virus associated intracranial lymphoma. Allergy. 2011;66:546. Conference abstract.
Picture 1

September 2026

CASE HISTORY

A 23 years old female underwent bilateral percutaneous nephrostomy (PCN) placement for nephrolithiasis. Following the procedure, the patient developed progressive right-sided hemiparesis, which subsequently worsened with the development of altered sensorium.

Section Editors

Dr. Arpita Sahu, Dr. Sarbesh Tiwari, Dr. Sabha Ahmed,

Dr. Smily Sharma, Dr. Meena Nedunchelian

Authors

Dr. Genesis Giddo Koodaly — Fellow, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

Dr. Adarsh Mohapatra — Fellow, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

Dr. Meghana Kancharla, Fellow, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

Dr. Vignavishal Nandakumar – DM resident, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

Dr. Gauri Bhimrao Bornak — Senior Resident, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

Dr. Jitender Saini — Professor and Head, Department of Neuroimaging and Interventional Radiology, NIMHANS, Bengaluru, India

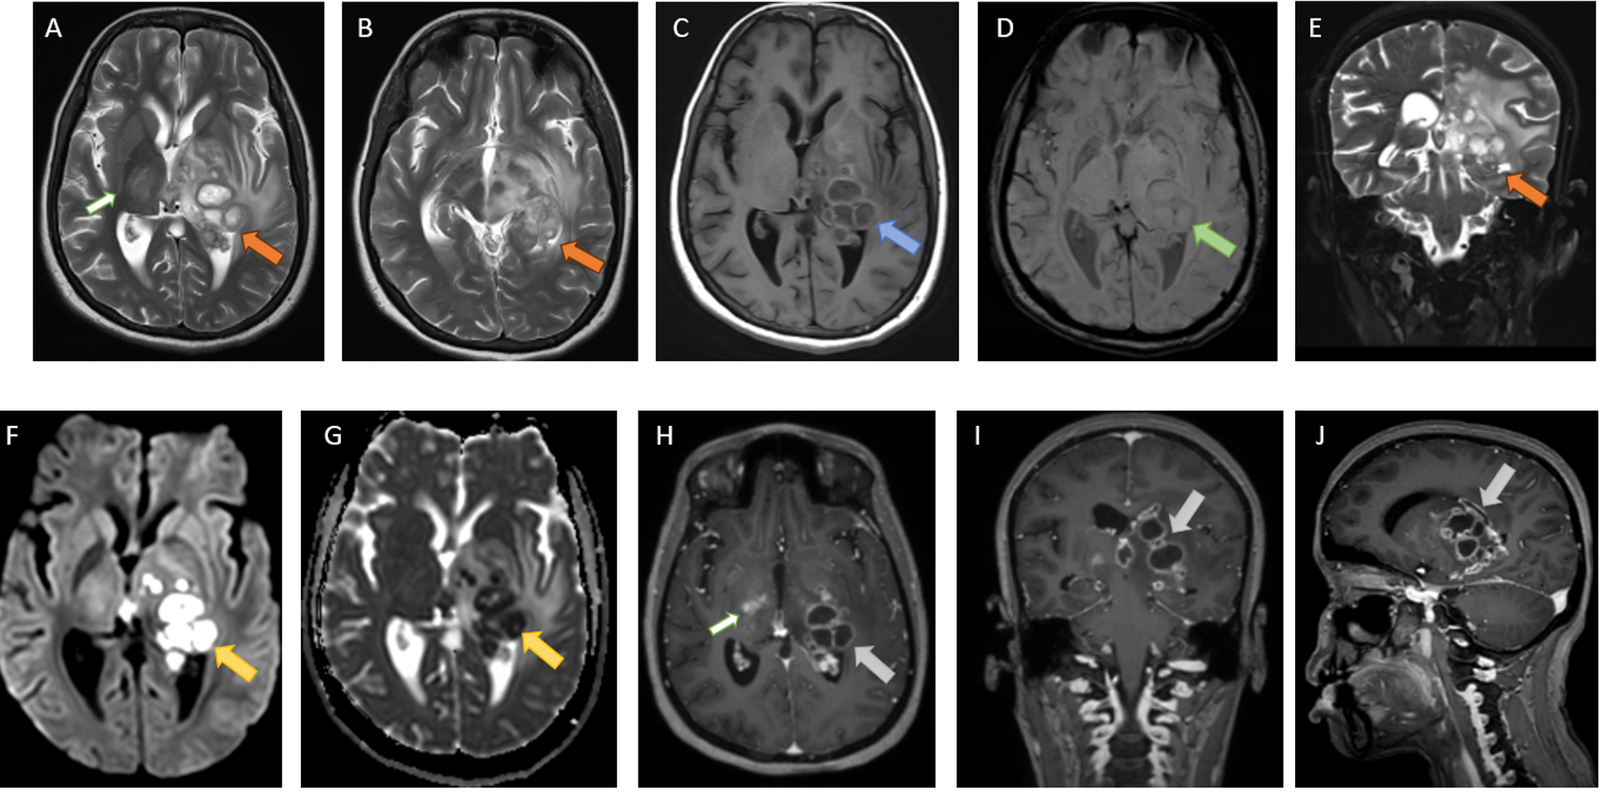
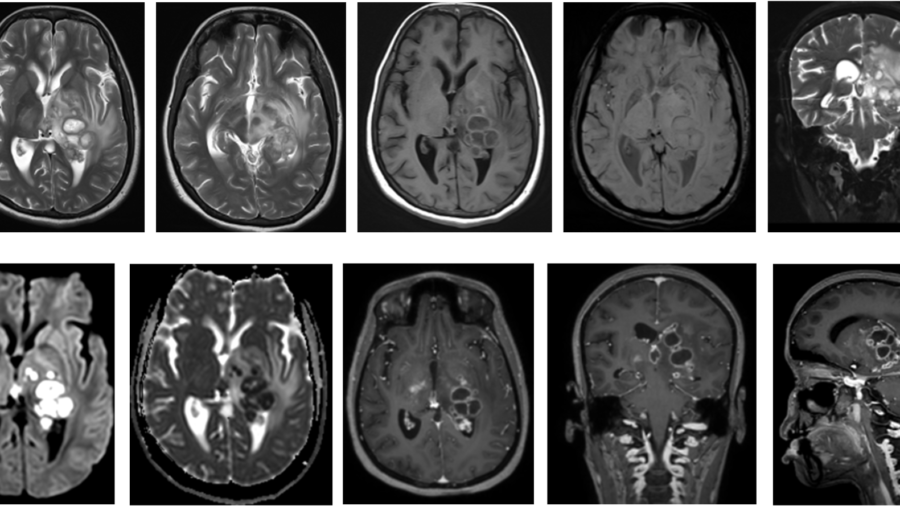
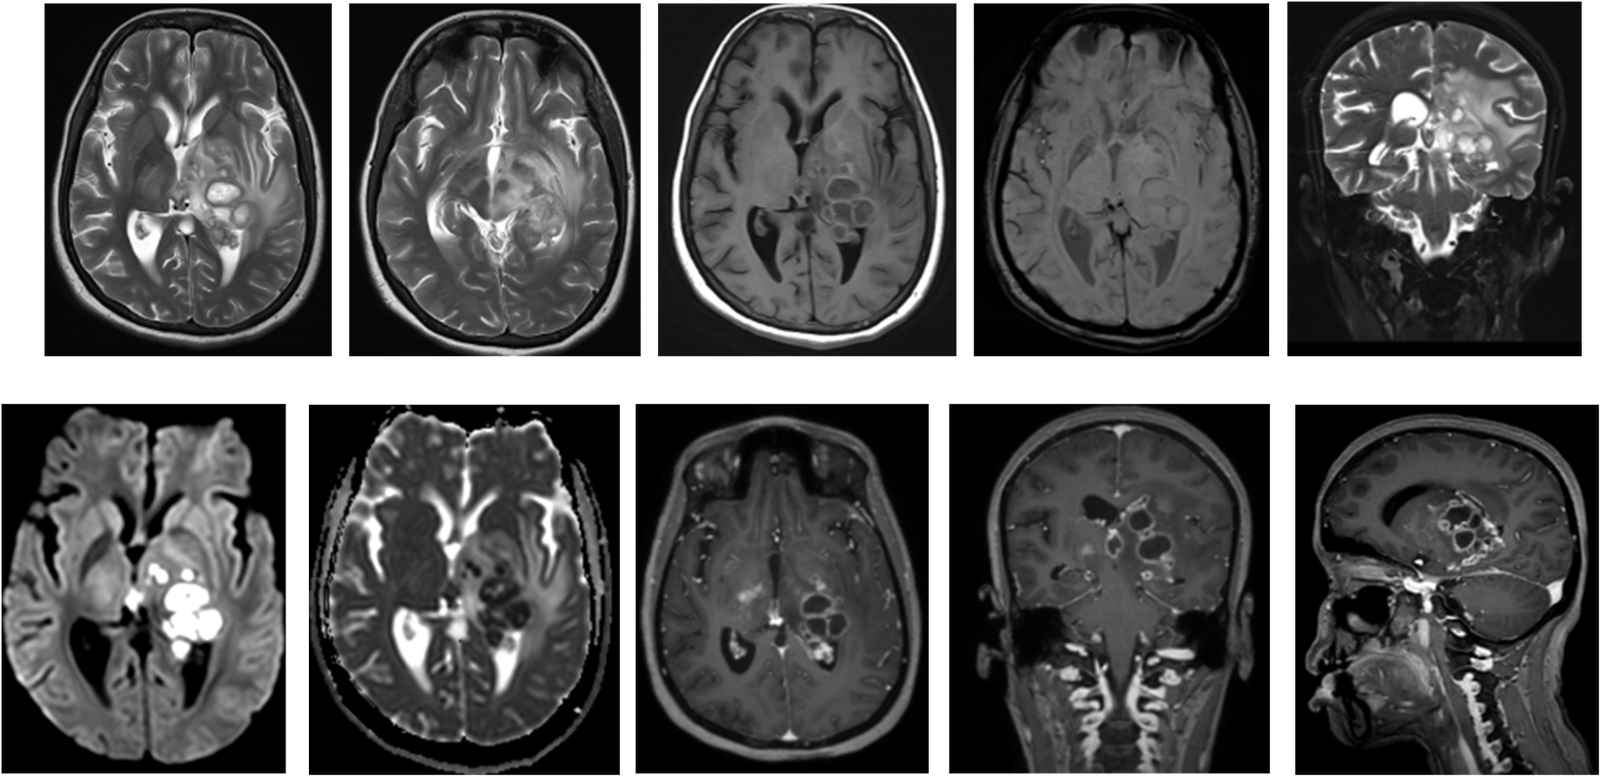
A–B: Axial T2; C: Axial T1; D: SWI; E: Coronal T2; F: DWI; G: ADC; H: Axial post-contrast T1; I: Coronal post-contrast T1; J: Sagittal post-contrast T1.

Multiple conglomerate and few discrete T2 hyperintense lesions are seen within the left thalamus and left medial temporal lobe, demonstrating a T2-intermediate signal intensity rim (orange arrows). The lesions show absent FLAIR suppression with both central and peripheral diffusion restriction (yellow arrows), resulting in expansion of the left thalamus. The lesion walls demonstrate intrinsic T1 hyperintensity (blue arrow). Patchy susceptibility blooming is seen on SWI (green arrow).

On post-contrast images, the lesions demonstrate peripheral enhancement with crenated margins (grey arrows). Few T2 hyperintense enhancing foci are seen in the right thalamic region (white arrows).

Significant perifocal vasogenic edema is seen extending into the left cerebral peduncle and hypothalamus, with resultant partial effacement of the left crural cistern and atrium of the left lateral ventricle. Mild upstream dilatation of the bilateral lateral ventricles is noted.

HISTOPATHOLOGY

Sections show small fragments of neuroparenchyma with a cyst wall thrown into folds, demonstrating extensive suppurative necrosis. The necrotic areas contain numerous fungal hyphae, which are long, slender, septate and branching, and are highlighted by Periodic acid–Schiff (PAS) and Grocott’s methenamine silver (GMS) stains.

The adjacent neuroparenchymal fragments show edema, along with chronic lymphocytic inflammation and scattered epithelioid histiocytes. Ziehl–Neelsen stain is negative for acid-fast bacilli.

Diagnosis: Necrotizing fungal inflammation (cerebral phaeohyphomycosis), consistent with Cladophialophora bantiana.

Cerebral phaeohyphomycosis is a rare but potentially fatal opportunistic fungal infection of the central nervous system caused by dematiaceous (melanized) fungi. Among these, Cladophialophora bantiana has a distinctive neurotropism and is an important cause of cerebral phaeohyphomycosis, particularly because infection may occur even in immunocompetent individuals. The route of CNS infection is predominantly hematogenous, with the lungs representing a potential portal of entry, although no primary extracranial focus may be demonstrable.

The imaging appearance is variable and may mimic other intracranial mass-forming lesions. Brain abscess formation is the most characteristic presentation, typically appearing as solitary or multiple lesions with surrounding vasogenic edema and variable rim enhancement. On MRI, the lesions are generally T2 hyperintense with a relatively hypointense or intermediate-signal capsule. Central diffusion restriction may be seen due to the high cellularity and viscous necrotic contents within the abscess cavity. Intrinsic T1 hyperintensity of the lesion wall, as observed in our case, may reflect the presence of melanin, proteinaceous contents, blood products, or a combination of these factors. Susceptibility effects, however, are variable and may be absent.

The presence of multiple conglomerate lesions with central diffusion restriction and a T2-intermediate rim suggested an infective abscess rather than a conventional neoplasm. The differential diagnosis of such lesions includes pyogenic abscess, tuberculoma, toxoplasmosis, metastases and high-grade glioma. Negative Ziehl–Neelsen staining in our case further argued against a mycobacterial etiology. Definitive diagnosis relies on histopathological examination and fungal identification.

The prognosis of cerebral C. bantiana infection remains poor, with high mortality despite antifungal therapy and surgical intervention. Early diagnosis, prompt surgical drainage or excision when feasible, and prolonged targeted antifungal therapy are important components of management.

Learning point: Cerebral phaeohyphomycosis should be considered in the differential diagnosis of rim-enhancing intracranial lesions with central diffusion restriction and disproportionate surrounding edema, even when the clinical history does not strongly suggest an invasive fungal infection.

References

1. Patil PN, Chavan R, Borse SS. Imaging in a rare case of cerebral phaeohyphomycosis caused by Cladophialophora bantiana in a renal transplant patient: a case report and the literature review. Egypt J Radiol Nucl Med. 2024;55:59. doi:10.1186/s43055-024-01229-8.

2. Rathod P, et al. Cerebral phaeohyphomycosis due to Cladophialophora bantiana in an immunocompetent individual: a case report and brief review of literature. Curr Med Mycol. 2020;6(2):52–57.

Picture 1

July 2026

CASE HISTORY

Patient of relapsed Early T cell precursor Acute lymphoblastic leukemia ( BM + testis) . He underwent Matched unrelated donor hematopoietic stem cell transplantation. He relapsed in CNS 3 months post transplant and is on weekly triple IT for CNS relapse. Now presented with altered sensorium and slurring of speach.

Section Editors

Dr. Arpita Sahu, Dr. Sarbesh Tiwari, Dr. Sabha Ahmed,

Dr. Smily Sharma, Dr. Meena Nedunchelian

Authors

Dr Prakhyath Gmabhira D

DNB resident, KMCH, Coimbatore.

Dr Kannan G,

Consultant, KMCH, Coimbatore

Evaluation

Sepsis workup, cerebrospinal fluid analysis, and serum electrolytes were normal, prompting evaluation for structural cause.

CT BRAIN:

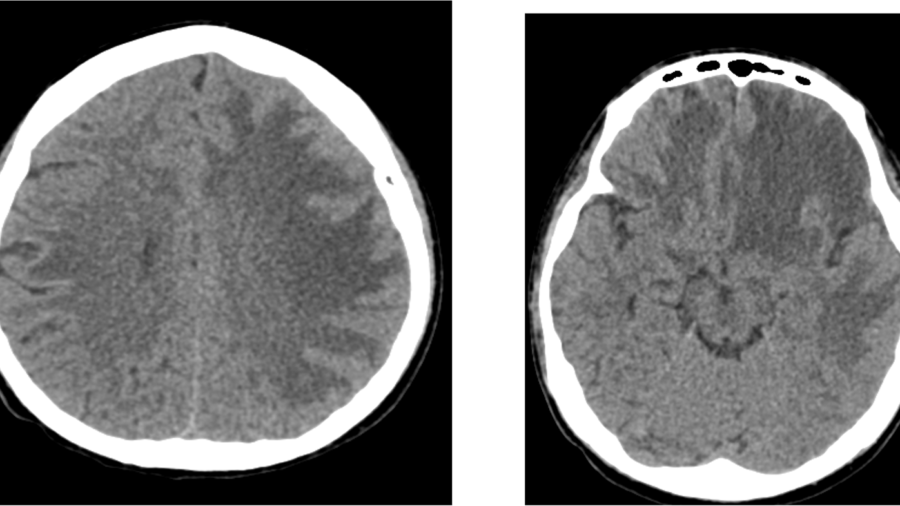
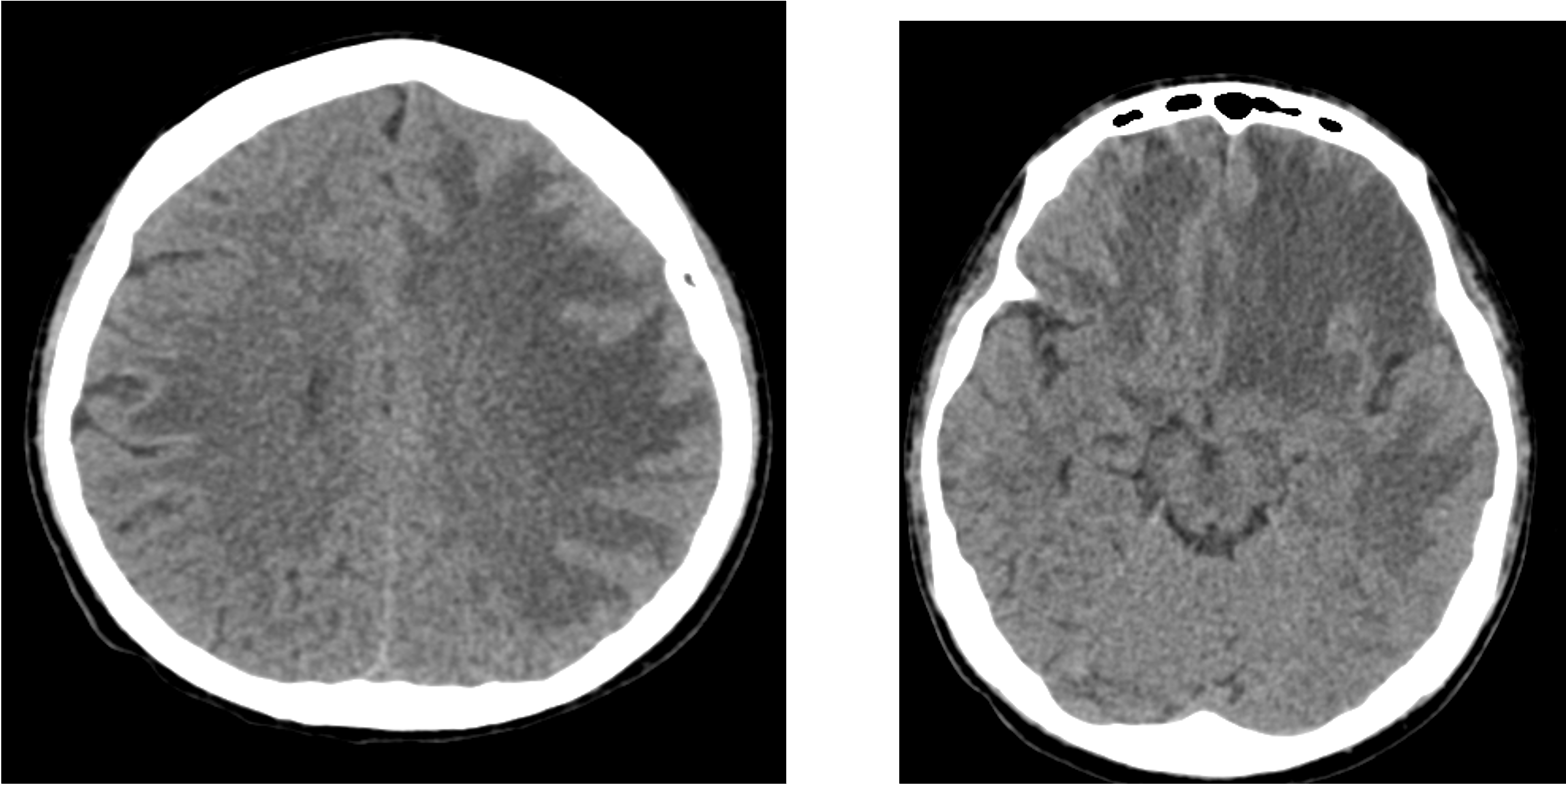
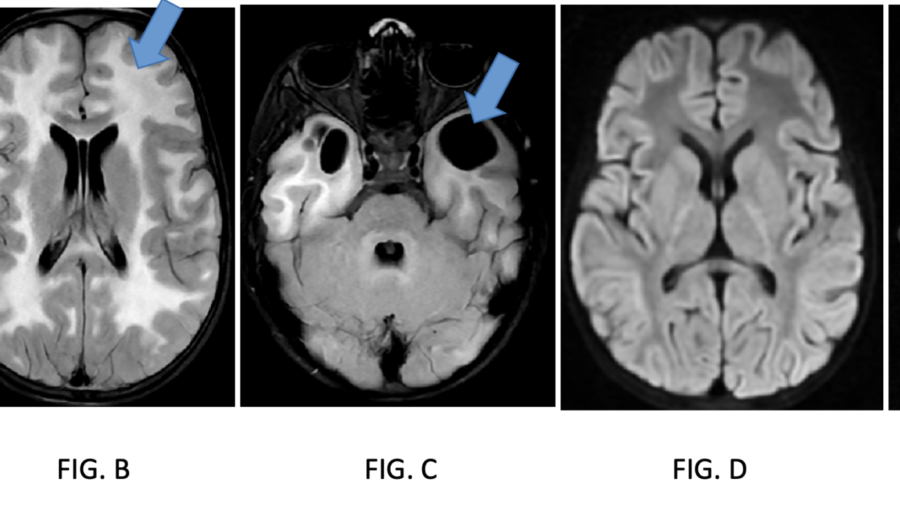
Bilateral confluent subcortical white matter hypodensities (left > right), involving fronto-parietal and temporal regions, with extension into the corpus callosum, associated with mild mass effect.

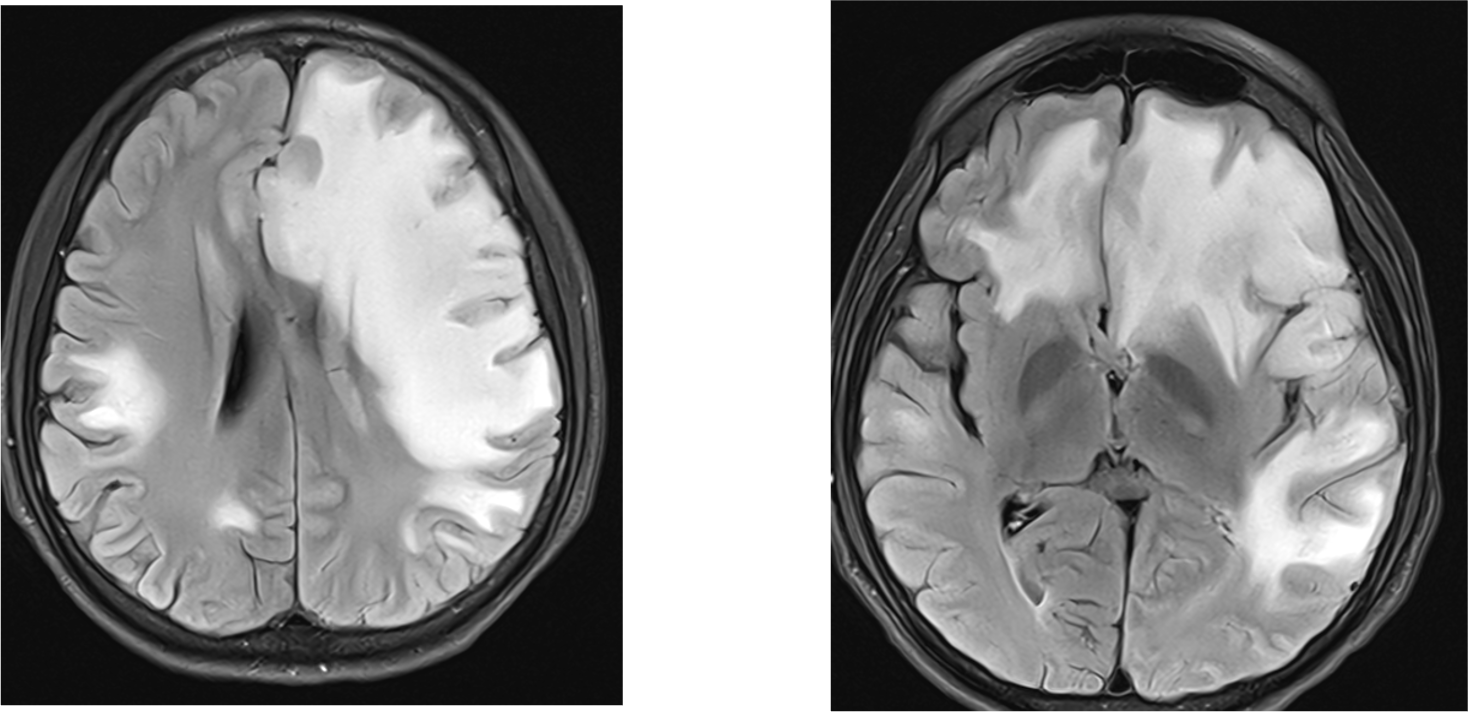
Diffuse infiltrative FLAIR hyperintense signal abnormalities involving:
 o Bilateral fronto-parietal subcortical white matter (L > R)
 o Anterior temporal subcortical white matter (L > R)
 o Left lentiform nucleus and external capsule
 o Periventricular white matter (trigone region)
 o Bilateral basifrontal regions (L > R)

T2-weighted linear hypointense areas noted within the lesions.

Patchy areas of diffusion restriction with associated blooming on SWI in the left frontal white matter.

Heterogeneous post-contrast enhancement involving the affected area are seen.

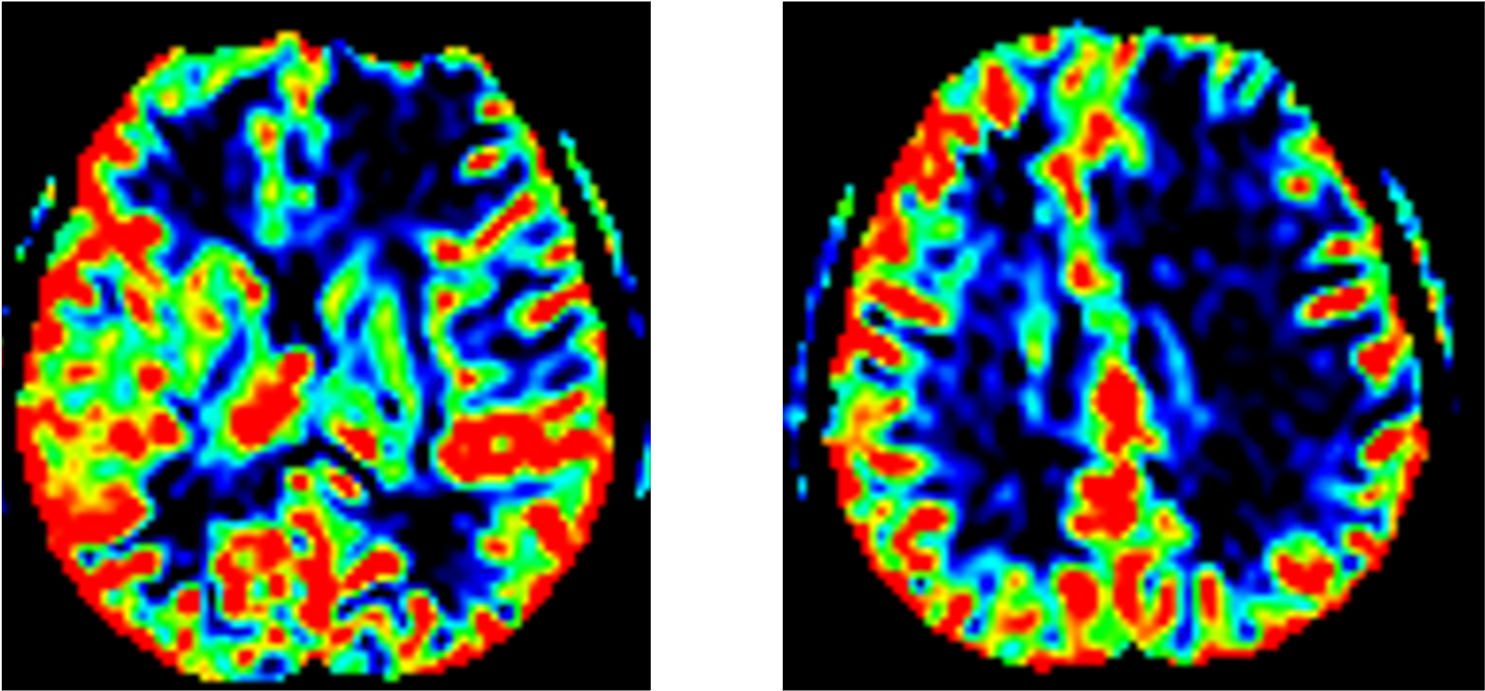
Significant reducedin cerebral blood volume (CBV) on perfusion imaging.

Imaging Differentials:

Angioinvasive fungal infection, likely invasive cerebral aspergillosis.

Other differentials- 1.leukemic infiltrates  2. PML

Diagnosis

High levels of Glactomannan in Bronchoalveolar lavage confirms Angio invasive cerebral aspergilosis

TREATMENT STARTED- INJECTION VARICONOZOLE.

After 1 week- SENSORIUM AND SPEECH IMPROVED.

ADVISE- CONTINUE ANTIFUNGAL.

Continued on voriconazole for 2 weeks and came for follow-up

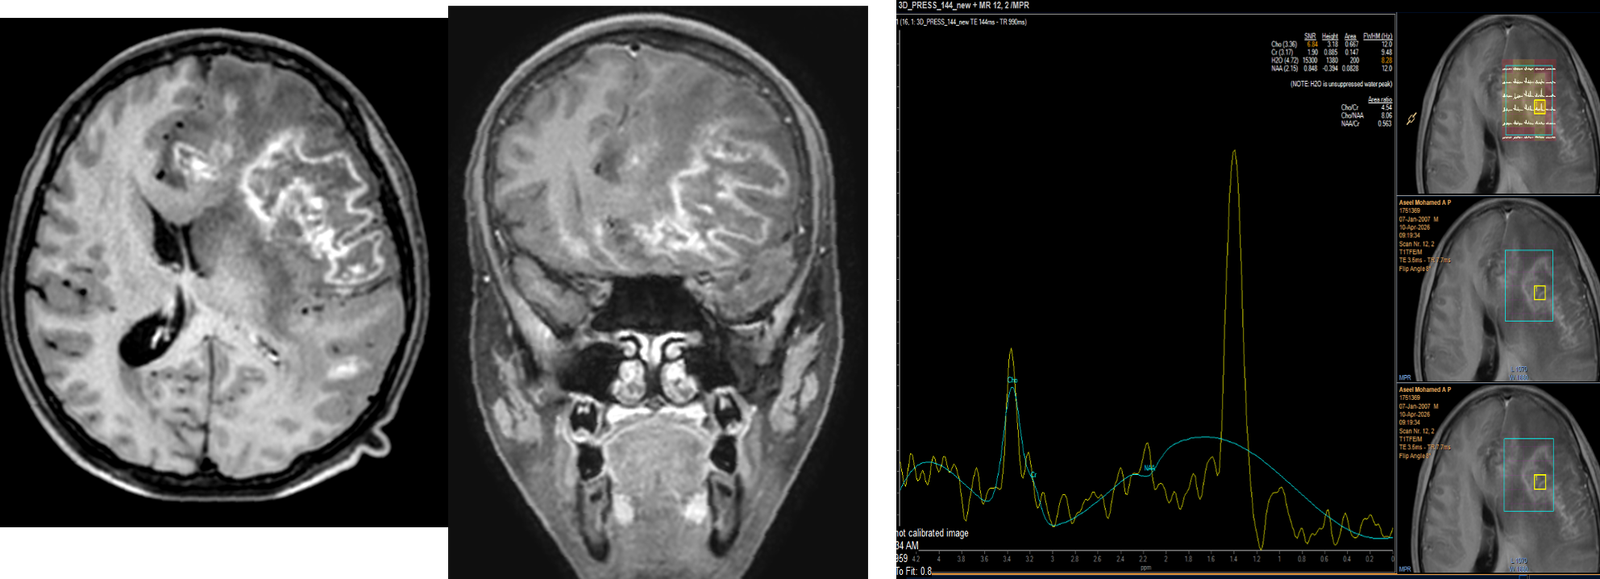
Interval increase in the patchy areas of diffusion restriction with peripheral SWI blooming are seen in left frontal lobe

Peripheral  enhancement are seen in left frontal lobe corresponding to areas of involvement, – likley evolving abscess.  MRS shows a prominent lipid-lactate peak.

FURTHER TREATMENT

Left frontotemporal craniotomy & excision biopsy done. Antifungal treatment continued.

CONCLUSION:

FeatureAngioinvasive AspergillosisCNS Leukemic InfiltratesProgressive Multifocal Leukoencephalopathy
PathophysiologyAngioinvasion causing vessel occlusion, infarction, and hemorrhage.CNS relapse with proliferation of leukemic blasts.JC virus opportunistic infection destroying oligodendrocytes (demyelination).
Primary LocationCorticomedullary junction, basal ganglia, thalami.Leptomeninges, cranial nerves, parenchyma.Asymmetric subcortical white matter (involves U-fibers).
Hemorrhage (SWI/T2)*Prominent. Blooming artifact due to micro/macro-hemorrhages.Typically absent.Absent.
Diffusion (DWI/ADC)Central restriction (due to ischemic/necrotic core).Variable restriction (due to hypercellularity of blasts).Usually absent (faint restriction possible at active advancing edge).
Enhancement (T1 C+)Ring or heterogeneous enhancement.Leptomeningeal or solid parenchymal enhancement.Non-enhancing (unless IRIS develops).
T2/FLAIR Signal“Target sign” (hyperintense core, dark rim, hyperintense edema).Homogeneous hyperintensity.Confluent, asymmetric hyperintensity.
T2 Internal ArchitectureLinear/nodular hypointensities (represents fungal elements and blood products).Homogeneous. Lacks dark internal bands.Homogeneous. Lacks dark internal bands.
Lab DiagnosticsElevated Galactomannan / Beta-D-glucan.Positive CSF cytology / Flow cytometry for ALL blasts.Positive JC Virus PCR in CSF.

Discussion

●Post-HSCT/Immunocompromised status.

●T2-Weighted Clues: Linear hypointense areas noted within the infiltrative lesions—a classic sign of fungal hyphae or angioinvasive architecture.

●SWI (Susceptibility): Patchy areas of “blooming” in the left frontal white matter, indicating micro-hemorrhages.

●DWI (Diffusion): Patchy areas of restricted diffusion, suggesting acute infarction or high cellularity.

●Heterogeneous enhancement with mass effect.

●Perfusion Imaging: No significant increase in Cerebral Blood Volume (CBV), helping to differentiate from high-grade neoplastic processes.

REFERENCE:

1.Matis GK, Voultsinou D, Chrysou O, Birbilis T, Geroukis T. Cerebral aspergillosis and acute myeloid leukemia. J Neurosci Rural Pract. 2013 Aug;4(Suppl 1):S134-5. doi: 10.4103/0976-3147.116459. PMID: 24174784; PMCID: PMC3808046.

2.1.Machaj W, Korbecki A, Bińczyk W, Siudek B, Ussowicz M, Zimny A. Atypical radiological presentation of fatal invasive cerebral aspergillosis in a patient with acute lymphoblastic leukemia after allogeneic bone marrow transplant: A case report. Radiology Case Reports [Internet]. 2025 Jun 26;20(9):4590–3. Available from: https://www.sciencedirect.com/science/article/pii/S1930043325005266

3.Chantelot, L., Sitterlé, E., Poirée, S. et al. Cerebral Aspergillosis: Diagnostic Challenges, Therapeutic Strategies, and Future Research. CNS Drugs 40, 43–58 (2026). https://doi.org/10.1007/s40263-025-01241-0.

‌

Picture 1

June 2026

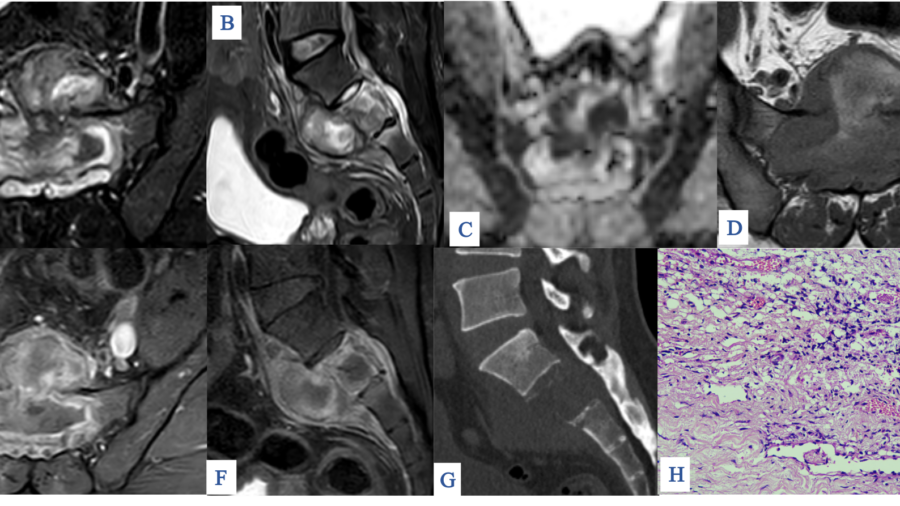
A 41-year-old male came with complaints of back pain radiating to both lower limbs which was gradually progressive, worsened on walking. Paresthesia in both lower limbs for 3 months. He developed urinary incontinence and constipation for 2 months.

There was no history of fever, cough, weight loss or loss of appetite. There was no history of trauma. On examination there was absent ankle jerk bilaterally and S1-S5 hypoaesthesia with perianal sensory loss.

Chest radiograph and abdominal screening showed no abnormality.

A plain CT and CE-MRI of the sacral spine were performed.